
Dental Radiology
CBCT, panoramic, and digital imaging centre.
- 3D CBCT
- Panoramic X-ray
- Low-dose, rapid results
First consultation free · same-day reply · no price pressure
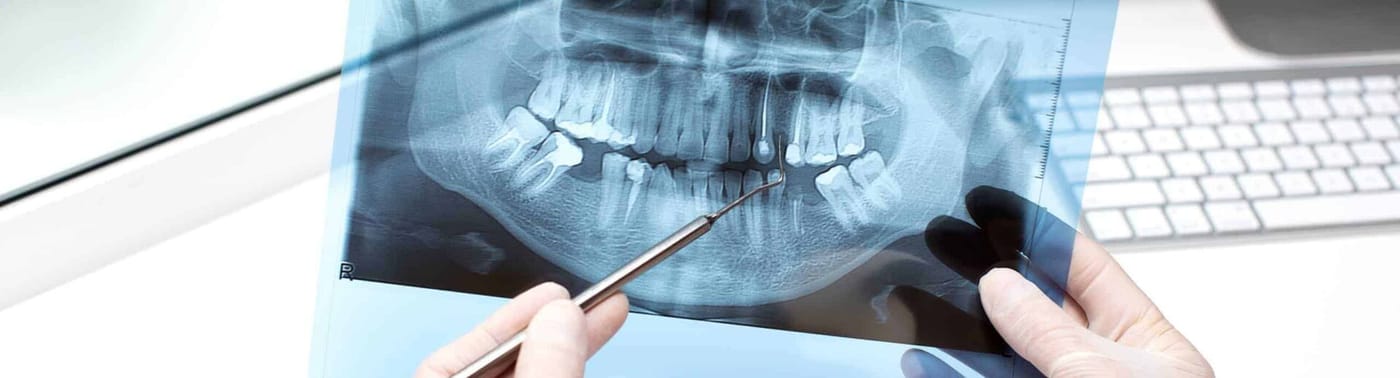
Dental radiology is a diagnostic service rather than a treatment, and which image is taken follows from the clinical question being asked. The dose gap between methods is large. Measured on a head phantom, a panoramic radiograph gave effective doses of 14.2 and 24.3 microsieverts on two units, and a four-image posterior bitewing set gave 5.0 microsieverts (PubMed 18762634). Pooling 20 published studies, mean adult effective dose from cone beam computed tomography was 84 microsieverts for a small field of view, 177 for medium and 212 for large, with very large differences between units, so a clinic quoting one number for a scan is oversimplifying (PubMed 25224586).
- 01Scan dose is a range, not a figure. In the same meta-analysis, adult effective doses ran from 46 to 1,073 microsieverts for large fields of view, 9 to 560 for medium and 5 to 652 for small, and for children 13 to 769 for large or medium fields and 7 to 521 for small (PubMed 25224586). Ask which field of view and which protocol a treatment plan assumes.
- 02The same examination can cost more than ten times the dose depending on technique: a full-mouth series measured 388 microsieverts with D-speed film and round collimation, against 34.9 microsieverts with photostimulable phosphor or F-speed film and rectangular collimation (PubMed 18762634).
- 03Whether a scan outperforms a plain radiograph depends on the question. Across 11 studies, pooled sensitivity and specificity for detecting vertical root fractures in unfilled teeth were 0.776 and 0.946 for cone beam CT against 0.425 and 0.939 for periapical radiographs, while in root-filled teeth cone beam CT sensitivity fell to 0.752 and specificity to 0.652 (PubMed 26699923).
- 04Imaging exists because clinical examination alone leaves gaps. A Cochrane review of 67 studies covering 19,590 tooth surfaces put the summary sensitivity of visual classification systems for enamel caries at 0.86 (95% CI 0.80 to 0.90) and specificity at 0.77 (95% CI 0.72 to 0.82); in a cohort of 1,000 surfaces with 28% prevalence that means 40 false negatives and 163 false positives, and the certainty of evidence was rated low (PubMed 34124773).
/ What is dental radiology?
Dental radiology is the imaging branch that supports diagnosis in dentistry. It is not a treatment in itself; it makes the tooth root, the jawbone, the joint and the neighbouring anatomy visible so the right treatment decision can be made. A tooth that looks sound on examination may hide an infection at its root tip; the gum may look healthy while the bone beneath it has receded. None of this shows in a mirror.
That is why imaging is a precondition of modern dentistry rather than a luxury. From implant planning to root canal treatment, from impacted wisdom teeth to orthodontic analysis, almost every comprehensive procedure starts with an image. The right image also prevents unnecessary work: when the problem is seen clearly, the treatment plan covers only what is needed.
| At a glance | |
|---|---|
| Duration | 1 session |
| Sessions | 1 |
| Warranty | · |
| Materials Used | CBCT 3D tomography · Panoramic X-ray · Periapical X-ray |
/ Which imaging methods are used?
A periapical X-ray is a small intraoral film showing one or a few teeth together with their roots; it is the first image taken for single-tooth problems. Bitewing films are strong at catching decay on the contact surfaces of back teeth. A panoramic X-ray gives an overview of both jaws, all teeth and the jaw joints in a single frame.
A cephalometric film shows the side profile of the skull with measurable angles and is the standard tool of orthodontic planning. Cone beam computed tomography (CBCT) is the three-dimensional member of this family: it shows bone layer by layer, with true thickness and depth. The imaging unit within Mosdent houses all of these methods under one roof, so patients are not referred elsewhere for a scan.
/ How does a panoramic X-ray differ from CBCT?
A panoramic X-ray is two-dimensional: it projects a three-dimensional anatomy onto a single plane. It is ideal for general screening; it quickly shows which tooth may be at fault, whether impacted teeth exist, and larger bone lesions. But because structures overlap, millimetre-level measurement and positional detail are limited.
CBCT removes that limit. Bone thickness, the exact course of the nerve canal, the three-dimensional angle of a root and the relationship to the sinus floor can only be measured reliably in a scan. That is why CBCT is preferred where millimetres matter, such as implant placement, impacted-tooth surgery and complex canal anatomy. The rule is simple: the image chosen is the one that answers the question at the lowest dose; if two dimensions are enough, three are not used.
/ Treatment Process
- 01Consultation: Initial examination and needs assessment; imaging where required.
- 02Treatment: Imaging per indication; reporting.
- 03Follow-up: Outcome review and aftercare guidance.
/ Which situation calls for which image?
For pain in a single tooth or a planned root canal, a periapical film answers most questions. When hidden decay is suspected between back teeth, a bitewing film is the most accurate tool. A general check-up, planning for missing teeth or assessment of wisdom teeth starts with a panoramic view. Jaw relationships before orthodontics are measured with cephalometric analysis.
CBCT is reserved for specific questions: is there enough bone volume for an implant, how close is an impacted tooth to the nerve, is a root fracture suspected, is the canal anatomy unusual? The clinical question, not the complaint, determines the image; that is why an examination always precedes the decision to scan.
/ How much radiation is involved, and is it safe?
Dental imaging is among the lowest-dose applications in medical radiology; intraoral films and panoramic X-rays are comparable to the natural background radiation received in daily life. CBCT doses vary across a wide band depending on the device, the field of view and the protocol, so speaking of a single CBCT dose is misleading. Measured dose figures, with their sources, are given in the quick answer and key points sections of this page.
The real guarantee of safety is protocol. The internationally accepted principle is to choose the lowest dose that answers the diagnostic question: digital sensors produce an image with less radiation than film, the field of view is collimated to the region of interest, and no exposure is made without an indication. Routine protective measures and periodic calibration of the devices are part of the same chain.
/ Is imaging done during pregnancy or for children?
During pregnancy, elective imaging is postponed until after birth where possible; for conditions that cannot wait, such as pain or infection, a narrow-field, low-dose intraoral film can be taken with protective measures. The decision is always made by the clinician, weighing benefit against risk. Even a suspicion of pregnancy should be shared with the team before any exposure.
In children, tissues are more sensitive to radiation than in adults, so the threshold for imaging is set even higher: an image is taken only when the examination leaves a question unanswered, the field is collimated as tightly as possible, and paediatric protocols are used. Bitewing films for hidden decay between primary teeth and panoramic views for monitoring development are used on clinical grounds.
/ How does the process work at the Mosdent imaging unit?
Because the imaging unit is inside the hospital, the scan is taken during the same visit, as a continuation of the examination. The clinician decides which image is needed, the exposure takes a few minutes, and the digital image appears on the clinician’s screen immediately. No outside appointment, film transport or second visit is required.
The image does more than answer that day’s question; it is stored in the patient’s digital file and becomes a baseline for later check-ups. Changes in bone level, the healing course of an infection or the adaptation around an implant can only be followed objectively when images taken over time are placed side by side.
- 1.Ludlow JB, Davies-Ludlow LE, White SC. Patient risk related to common dental radiographic examinations: the impact of 2007 International Commission on Radiological Protection recommendations regarding dose calculation. J Am Dent Assoc 2008;139:1237-43. PubMed 18762634
- 2.Ludlow JB, Timothy R, Walker C, Hunter R, Benavides E, Samuelson DB, et al. Effective dose of dental CBCT-a meta analysis of published data and additional data for nine CBCT units. Dentomaxillofac Radiol 2015;44:20140197. PubMed 25224586
- 3.Talwar S, Utneja S, Nawal RR, Kaushik A, Srivastava D, Oberoy SS. Role of Cone-beam Computed Tomography in Diagnosis of Vertical Root Fractures: A Systematic Review and Meta-analysis. J Endod 2016;42:12-24. PubMed 26699923
- 4.Macey R, Walsh T, Riley P, Glenny AM, Worthington HV, O'Malley L, et al. Visual or visual-tactile examination to detect and inform the diagnosis of enamel caries. Cochrane Database Syst Rev 2021;6:CD014546. PubMed 34124773

Who is this treatment for?
- Need for accurate diagnosis before treatment
- Detection of problems in the mouth, teeth, and jaw
- Complex cases requiring implant planning
- Evaluation of impacted teeth
- Evaluation of canal anatomy
Doctors specialising in this treatment





Frequently asked
01What is the difference between CBCT and a standard panoramic X-ray?+
A panoramic X-ray provides a two-dimensional overview. CBCT (cone beam computed tomography) produces three-dimensional, layered images. Far more informative for complex cases such as implant planning, impacted teeth, and canal anatomy.
02Is the radiation dose safe?+
The digital sensors and low-dose protocols used at our clinic result in an extremely low radiation dose. Comparable to the natural background radiation encountered in daily life. A digital sensor is a receptor that needs less radiation than film to produce the same image.
Restorative & General
Speak with your doctor about this treatment.
Not sure which treatment fits? Tell us what’s wrong →