A laminate veneer is a thin ceramic or composite shell, roughly 0.2 to 0.5 mm thick, bonded to the front surface of a tooth with little or no enamel reduction. That thickness is what separates it from a conventional porcelain veneer at 0.5 to 1.0 mm and a crown at 1.5 to 2.0 mm, which covers the tooth on all sides. Survival is documented: a meta-analysis of 29 clinical studies reported pooled survival of 96.13 percent for feldspathic, 93.70 percent for leucite-reinforced and 96.81 percent for lithium disilicate laminate veneers at 10.4 years, with no significant difference between materials (PubMed 39523553).
- 01Laminate veneers sit at 0.2 to 0.5 mm, conventional porcelain veneers at 0.5 to 1.0 mm and crowns at 1.5 to 2.0 mm, so laminates remove the least tooth structure.
- 02Pooled survival at 10.4 years was 96.13 percent for feldspathic, 93.70 percent for leucite-reinforced glass ceramic and 96.81 percent for lithium disilicate veneers across 29 studies; zirconia showed 100 percent survival but only at 2.6 years, with no long-term data (PubMed 39523553).
- 03Complication rates separate the materials more sharply than survival does: at 10.4 years technical complications ran 41.48 percent for feldspathic, 29.87 percent for leucite-reinforced and 6.10 percent for lithium disilicate (PubMed 39523553).
- 04An earlier meta-analysis of 13 studies put cumulative survival at 89 percent, 95 percent CI 84 to 94, over a median 9 years, with fracture or chipping at 4 percent and debonding at 2 percent as the leading events (PubMed 26757327).
- 05Candidacy is bounded by enamel and bite. Laminates bond to enamel, so untreated decay, active gum disease, severe enamel erosion and unmanaged bruxism are standard exclusions.
What a Laminate Veneer Is
A laminate veneer is a thin, custom-made shell of ceramic or composite resin, roughly 0.2 to 0.5 mm thick, bonded to the front surface of a tooth with little or no enamel removed. Because of that thickness it is often compared to a contact lens. The shell changes the colour, shape and surface of the visible part of the tooth while the rest of the tooth stays as it was. The treatment is also called no-prep or minimal-prep veneers, and it is described in more detail on the laminate teeth veneers treatment page. The version bonded with no enamel reduction at all has its own page, prepless laminate veneers.
The idea behind laminates is conservation. Conventional porcelain veneers and crowns are thicker and need more of the tooth to be reduced so that the restoration sits flush with the neighbouring teeth. Laminates are thin enough to be bonded over a largely intact enamel surface. In practice the enamel is usually lightly roughened and etched so that the bonding material can grip it, and in some cases a small amount of reshaping is still needed where a tooth sits forward of its neighbours.
Laminate veneers have moved from a niche cosmetic option into routine use over the past decade, largely because patients prefer treatments that keep their own tooth structure. The approach also brings limits. A very thin shell depends on a healthy enamel surface underneath and on a bite that does not overload it. It changes how teeth look, and it has limited power to change where teeth sit. Understanding both sides helps a patient judge whether laminates fit their situation or whether another approach would serve them better.
The sections that follow compare laminates with thicker restorations, describe who is a suitable candidate, walk through the clinical steps and set out what published studies report about how long laminates last and which problems they develop.
Cosmetic Problems Laminate Veneers Can Correct
Laminate veneers are used for changes that sit mainly on the surface of the front teeth. Mild discoloration is a common reason, particularly staining that has not responded to whitening, such as grey or banded colour changes inside the enamel. Because the shell covers the front surface, it can mask these colours while giving the tooth a uniform shade.
Small chips and minor cracks in the enamel are another group. A thin veneer can rebuild a chipped edge and restore the outline of the tooth without a crown. Minor gaps between teeth, known as diastemas, can be closed by making the veneers slightly wider than the original teeth, as long as the gap is small enough that the teeth do not end up looking oversized.
Slight crookedness or rotation can be disguised when the tooth is only a little out of line. The veneer is shaped to follow the ideal arch line, so the smile looks straighter even though the tooth itself has not moved. When teeth are clearly crowded, rotated or tipped, orthodontic treatment usually comes first, since forcing a veneer over a badly positioned tooth would require heavy reduction.
Uneven tooth shape or size is also a common indication. Teeth that are small, pointed, uneven in length or worn at the edges can be brought into proportion with each other. Worn enamel from grinding or acid erosion is sometimes included in this group, but it needs care. Wear caused by grinding means the forces that damaged the teeth will also act on the veneers, and erosion may have left too little enamel for a reliable bond. In both situations the cause is assessed before any veneer is planned.
For people who want a brighter or more even smile without committing to heavy tooth reduction, laminates offer a natural-looking finish while keeping most of the original tooth intact.
Thickness and Preparation Compared With Veneers and Crowns
The defining difference between laminates, conventional veneers and crowns is thickness, and thickness decides how much of the tooth has to be removed. Laminate veneers are typically 0.2 to 0.5 mm thick. Conventional porcelain veneers run 0.5 to 1.0 mm and need moderate enamel reduction so that they do not look bulky. A crown is 1.5 to 2.0 mm thick and covers the tooth on every surface, so the tooth is reduced on all sides.
Enamel removal follows the same order. Laminates need little or no reduction, conventional veneers need a measured layer removed from the front surface, and crowns need the most. This matters because enamel does not grow back. Once a tooth has been shaped for a crown, it will need a crown for the rest of its life.
The chair time and procedure differ as well. Laminate preparation is often so limited that local anaesthesia is unnecessary, although it is offered to patients with sensitive teeth. Conventional veneers usually involve anaesthesia and temporary veneers while the final ones are made. Crowns involve preparation, an impression or scan, a temporary crown and a second visit to fit the final crown.
Each option has its place. Laminates suit mild to moderate cosmetic changes on healthy teeth. Conventional veneers allow more change in shape and colour, and they are chosen when a tooth needs more reshaping or when dark discoloration needs a thicker layer to hide it. Crowns are used when a tooth is heavily filled, broken down or weakened, because they protect the whole tooth. Appearance can be very natural with all three when they are well made. The choice depends on the condition of the tooth, the size of the change the patient wants and how much tooth structure can be preserved.
Why Enamel Matters for Bonding
Laminate veneers rely on adhesion, and adhesion to enamel is stronger and more predictable than adhesion to the dentin underneath it. Enamel is a dense, highly mineralised layer; when it is etched, it forms a microscopic surface that bonding resin locks into. Dentin contains more water and organic material, which makes the bond more demanding. For this reason the planning of a laminate case aims to keep the whole preparation, including its margins, within enamel.
Published data show how much this choice matters. In a retrospective study of 580 porcelain laminate veneers followed for up to 12 years, veneers bonded to dentin, or with preparation margins in dentin, were approximately 10 times more likely to fail than veneers bonded to enamel (PubMed 23342345). The same study reported a survival rate of 99% for veneers with preparations confined to enamel and 94% for veneers with enamel only at the margins (PubMed 23342345). Across the whole group, the overall cumulative survival was 86%, and fracture was the most frequent type of failure (PubMed 23342345). A two-year clinical study of 125 porcelain laminate veneers in 28 patients reported 91.2% overall survival, and veneers bonded to severely exposed dentine were more likely to fail than those bonded to enamel or to enamel with minimal dentine exposure (PubMed 25279393).
These findings shape several clinical decisions. Teeth with thin enamel, from erosion, heavy brushing or age, may not have enough enamel left for a reliable laminate. A tooth that already sits forward in the arch may need only surface preparation, while a tooth that sits back may need no preparation at all. Where a tooth has old composite fillings on the front surface, the dentist assesses how much of the bonding area will be enamel and how much will be filling material.
Enamel preservation also affects what happens later. A laminate bonded to intact enamel can often be replaced with a similar thin shell if it is damaged, since the tooth underneath has changed very little.
Who Is a Suitable Candidate
Laminate veneers work well for people whose teeth and gums are already healthy and who want subtle to moderate cosmetic change. The first requirement is enough enamel. Because the shell bonds directly to the outer enamel layer, a tooth with intact, minimally worn enamel gives the most reliable bond. If there is not enough healthy enamel, the bond may weaken and the veneer may fail early.
The second requirement is a suitable bite. Mild imperfections in the way teeth meet are acceptable, but a deep overbite, a crossbite or edge-to-edge contact on the front teeth can put extra load on thin veneers and lead to chipping or debonding over time. The bite is examined with the teeth closed, during side-to-side movements and while biting forward, to see where the veneers would take load.
Good oral hygiene and dental health are the third requirement. The gums should be healthy and free of active inflammation, and there should be no untreated decay. Veneers are not placed over cavities or inflamed gum tissue, because the margins of the veneer sit close to the gum line and need a clean, stable environment. Patients with gum disease are treated first, and veneers are planned once the gums have settled.
Realistic goals complete the picture. Laminates are well suited to correcting mild discoloration, small chips, minor gaps and uneven edges. They are less suited to drastically reshaping teeth or repositioning them. Smoking is also relevant. It can stain the margins of veneers and increases the risk of gum problems, which in turn can affect the bond and the appearance around the gum line. Patients who smoke are advised about these effects before treatment, and stopping or reducing smoking improves the outlook.
When Laminate Veneers Are Not Suitable
Some conditions rule out laminate veneers or require them to be postponed until the underlying problem is managed. Grinding or clenching is the most frequent concern. Night-time grinding and frequent clenching place heavy, repeated force on the front teeth, and thin laminates are vulnerable to cracks, chips and full debonding under that load. When bruxism is mild and controlled with a nightguard, veneers may still be considered after a careful assessment of the bite.
Active tooth decay and gum disease must be treated before any cosmetic work. Placing veneers over compromised teeth can hide ongoing damage and lead to failure of the veneer as the tooth underneath deteriorates. After treatment, the teeth and gums are given time to stabilise before veneers are planned.
Severely misaligned or heavily damaged teeth are another limit. Large gaps, marked rotations and broken-down teeth may need more coverage or support than a thin shell can provide. In these cases orthodontic treatment, conventional veneers or full crowns may be more suitable, sometimes in combination.
Thin or worn enamel is the fourth limit. Patients with significant erosion from acid reflux, frequent acidic drinks or overbrushing, or with enamel lost through earlier dental treatment, may not have enough surface for a reliable bond. The cause of the erosion is identified and managed first, both to protect the remaining teeth and to judge whether bonding is still possible.
A thorough dental assessment, including radiographs and a bite evaluation, is needed to decide whether a patient is a good candidate. People with more complex dental needs can still achieve a smile transformation, but their plan may involve conventional veneers or other restorative procedures in place of laminates.
Planning, Smile Design and Shade Selection
Treatment begins with a consultation and a planning phase that is often supported by digital smile design. Photographs, video and a digital scan are used to map facial proportions, the lip line, the position of the natural teeth and the line of the smile. Software then creates a virtual preview of the planned result. This preview helps the dentist and patient agree on tooth length, width and shape before anything is done to the teeth.
A physical trial of the design, known as a mock-up, is often made from the preview. Tooth-coloured material is placed temporarily over the teeth so that the patient can see and feel the planned shape in their own mouth, speak with it and look at it in photographs. Changes are easy to make at this stage and much harder later.
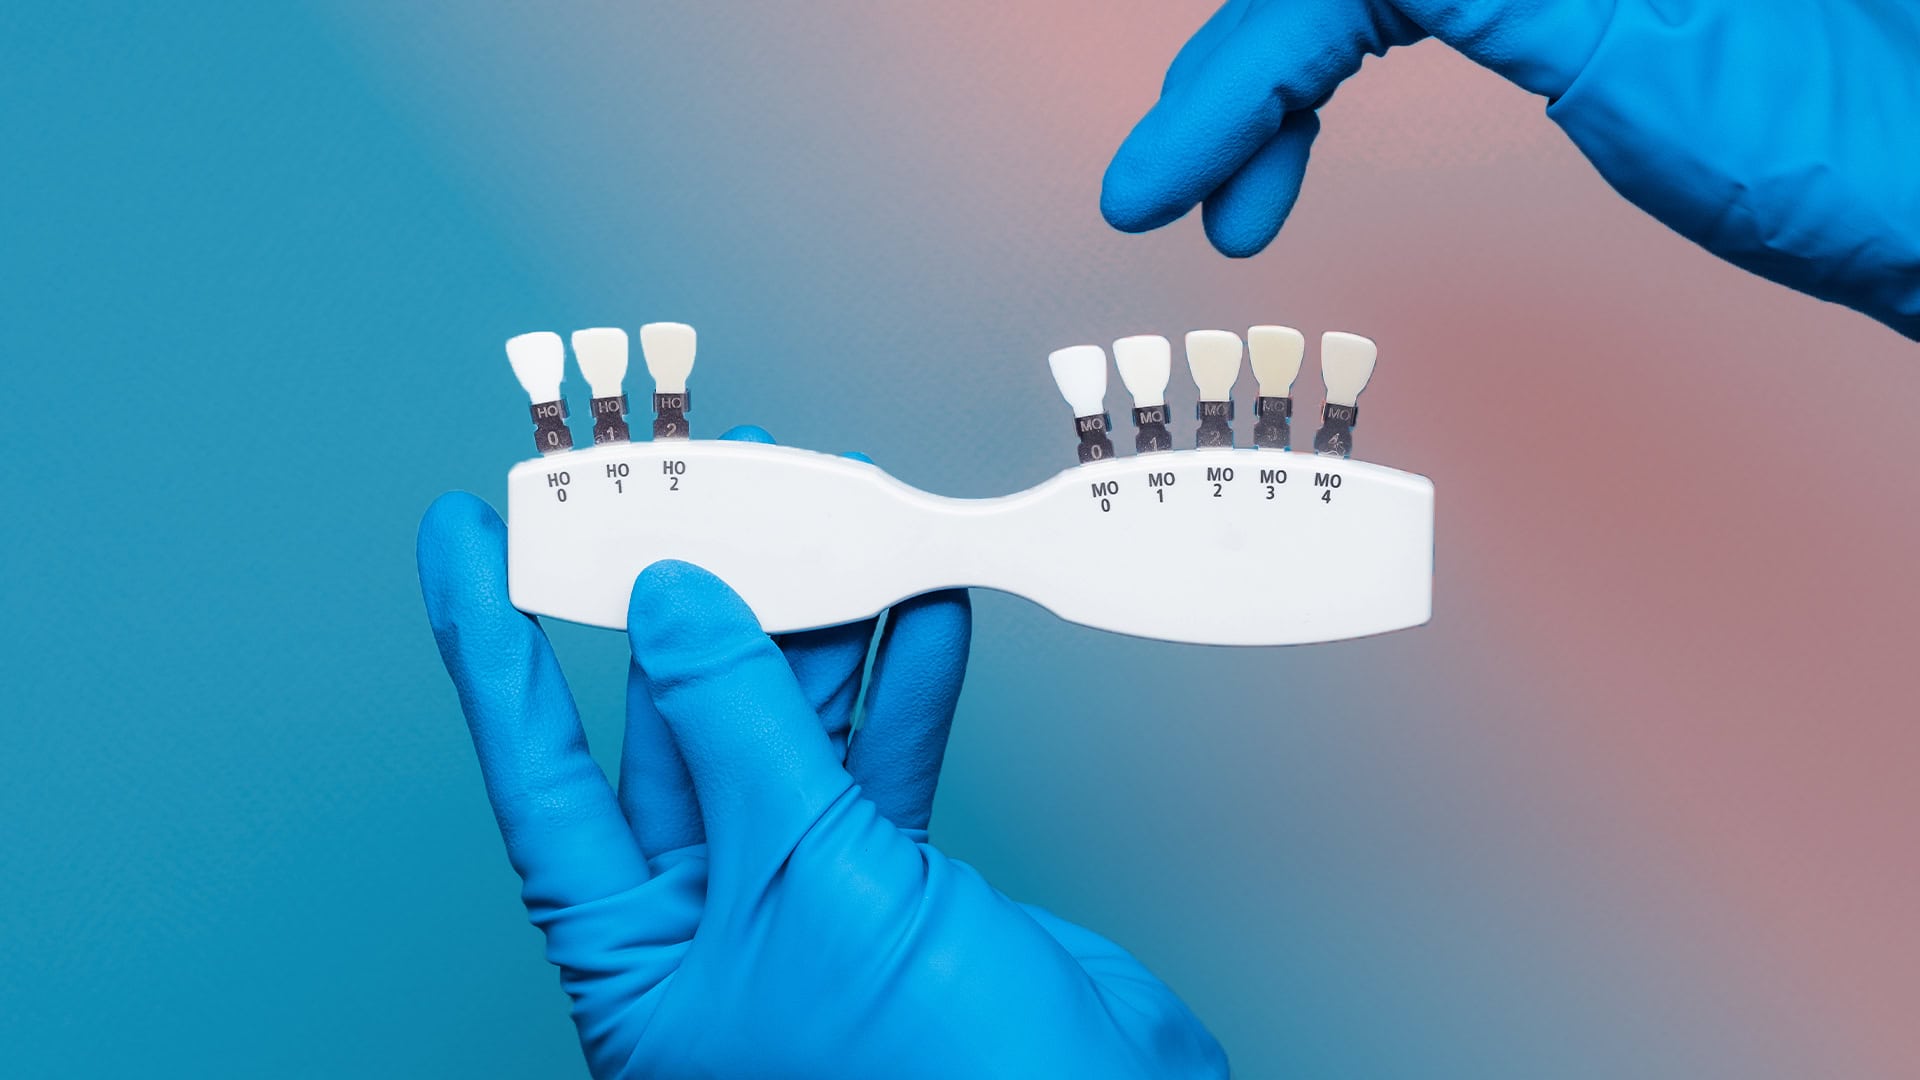
Shade selection is part of the same visit. The aim is a shade that looks bright and healthy while staying realistic, so that the teeth do not look artificial. This matters most when only a few front teeth are being treated and the veneers must blend with untreated neighbours. Shade tabs, photographs under standard light and digital shade tools help match the veneers to the surrounding teeth.
Whitening is usually completed before veneers are made. Ceramic veneers keep the shade they were made in, while natural teeth can lighten with bleaching. If the natural teeth are whitened after the veneers are placed, the veneers may then look darker than their neighbours. For this reason teeth whitening is normally done first, and the veneer shade is chosen once the natural teeth have reached a stable colour.
The number of veneers is also decided during planning. Some patients need only one or two teeth treated, while others choose a set across the upper front teeth so that the smile looks uniform. The decision depends on how many teeth are visible when the patient smiles broadly.
Scanning, Try-In and Bonding
Once the design is agreed, the teeth are prepared as the plan requires. In many laminate cases this means only a light roughening of the enamel surface, and some teeth may need no preparation at all. Local anaesthesia is often unnecessary, though it is available for patients with sensitive teeth or where a small amount of reshaping is required.
Instead of traditional impression material, many clinics use a digital intraoral scan. The scanner records the teeth in three dimensions, and the model is sent to the dental laboratory where the veneers are made. The fabrication time depends on the material and the complexity of the case, and on whether the laboratory works from a digital or a physical model. When the teeth have not been reduced, temporary veneers are usually unnecessary, which makes the waiting period more comfortable and discreet.
When the veneers arrive, a try-in session comes first. The veneers are placed on the teeth without permanent bonding, often with a coloured try-in paste, so that fit, alignment and colour can be checked. The patient sees the result in the mirror before anything is fixed. Small adjustments to shape can be made at this point.
Bonding follows a careful sequence. The tooth surface is cleaned and etched to create a micro-rough surface, a bonding agent is applied and the veneer is seated with a resin cement. A curing light hardens the cement, excess material is removed from the margins, and the edges are polished so that the transition between veneer and tooth is smooth. Isolation of the teeth from saliva during this step is important for the bond.
After bonding, the bite is checked in all movements and adjusted where needed. Most patients can return to normal activities immediately. A follow-up visit is usually arranged to check the gums around the new veneers and to confirm that the bite feels comfortable once the patient has adapted to the new shape.
Ceramic and Composite Materials
Laminate veneers are made either from ceramic or from composite resin, and the choice affects appearance, durability and maintenance. Ceramic laminates are made in a laboratory from materials such as feldspathic porcelain, leucite-reinforced glass ceramic or lithium disilicate, the material used in e.max restorations. These materials have good translucency and resist staining and wear, which helps them keep their appearance over many years.
Composite laminate veneers are made from tooth-coloured resin, either directly on the tooth in the clinic or indirectly in the laboratory. They need less time and can be repaired easily, but the surface is softer. Published data reflect this difference. A systematic review of resin composite laminate veneers found a pooled survival of 88% in randomised trials, with mean follow-up times ranging from 24 to 97 months (PubMed 38035903). Surface roughness, colour mismatch and marginal discoloration were the most frequently reported complications, and the review found higher survival for direct composite veneers than for the indirect approach (PubMed 38035903).
A direct comparison of the two material groups exists. A randomised split-mouth trial placed 46 laminate veneers in 10 patients, 23 made of indirect resin composite and 23 of ceramic, and followed them for up to 3 years (PubMed 23534025). Survival was 87% for the composite group and 100% for the ceramic group, a difference that was not statistically significant, and the overall survival rate was 93.5% (PubMed 23534025). Slight staining at the margins and rough surfaces were more frequently observed in the composite veneers (PubMed 23534025).
In practice, ceramic is usually chosen when long-term appearance and stain resistance are priorities, while composite may be chosen as a more conservative or shorter-term solution, for younger patients or for small corrections. Composite veneers generally need polishing, repair or replacement sooner than ceramic ones, and patients choosing them are told to expect this maintenance.
Survival Over Ten Years and Beyond
The lifespan of ceramic laminate veneers has been studied in large clinical reviews. A meta-analysis of 29 studies reported pooled survival at 10.4 years of 96.13% for feldspathic, 93.70% for leucite-reinforced glass ceramic and 96.81% for lithium disilicate laminate veneers, and it found no difference between these materials (PubMed 39523553). Zirconia laminate veneers showed a 100% survival rate with no complications at 2.6 years, but no long-term data were available for them (PubMed 39523553).
Long follow-up of a single material shows how survival changes over time. In a study of 413 pressed lithium disilicate veneers, the probability of survival was 98% after 5 years, 95% at 10 years, 91% at 15 and 87% at 20 years (PubMed 31168916). Complications occurred in 3.63% of the restorations in that series (PubMed 31168916).
An earlier meta-analysis gives a similar picture. Across 13 studies with a median follow-up of 9 years, the estimated overall cumulative survival of ceramic laminate veneers was 89%, with 94% for glass ceramic and 87% for feldspathic porcelain (PubMed 26757327). The differences between these reviews reflect the studies included, the materials and the follow-up periods, but all of them describe high survival over many years.
These figures describe groups of veneers placed under study conditions. An individual veneer can last longer or shorter depending on the bite, grinding habits, accidental trauma, the quality of the bond to enamel and how well the margins are kept clean. Survival also means that the veneer is still in place. A veneer can remain in the mouth and still need polishing, a small repair or attention at its margin during that time, which is why complication rates are considered separately.
Complications and Signs That Replacement Is Needed
Complication rates separate the materials more clearly than survival does. In the 29-study meta-analysis, technical complication rates at 10.4 years were 41.48% for feldspathic, 29.87% for leucite-reinforced glass ceramic and 6.1% for lithium disilicate laminate veneers (PubMed 39523553). The authors concluded that lithium disilicate slightly outperforms the other two materials with lower long-term complication rates (PubMed 39523553).
The type of event matters too. In the meta-analysis of 13 studies, fracture or chipping was the most frequent complication at 4%, followed by debonding at 2%, severe marginal discoloration at 2%, endodontic problems at 2% and secondary caries at 1% (PubMed 26757327). Fracture or chipping is therefore more common than a veneer coming off entirely.
Several signs indicate that a veneer needs attention or replacement. Wear or chipping at the edge, especially on teeth that take the most contact during biting, is one of them. Debonding or lifting at a margin can trap bacteria and allow decay to start underneath, so a veneer that feels rough or catches floss at its edge is checked promptly. A colour mismatch between veneers and natural teeth can appear over time, particularly if the natural teeth are whitened after the veneers are placed. Gum recession can expose the edge of the veneer and the tooth beneath it, which changes the appearance at the gum line. Fractures from accidents or sports injuries are a further cause.
In most cases an individual veneer can be replaced without redoing the whole smile. When several veneers were made together as part of a larger design, replacing a single one requires careful shade matching, and some patients prefer to renew a group together for a consistent look.
Daily Care and Protective Habits
Laminate veneers are durable, but they are thinner than conventional restorations, and daily habits have a large effect on how long they last. Cleaning is the foundation. Brushing twice a day with a soft-bristled brush and a non-abrasive fluoride toothpaste protects both the veneer surface and the margin where it meets the tooth. Gritty whitening pastes, including those with baking soda or charcoal, can dull the glaze of ceramic and roughen composite, so they are avoided. Flossing every day removes plaque at the gum line and between veneers, where decay and gum inflammation would otherwise begin.
Biting habits are the next consideration. Hard foods such as nuts, ice, hard sweets and raw carrots can chip veneers, especially when bitten with the front teeth; cutting such foods into smaller pieces and chewing them with the back teeth reduces the risk. Using teeth to open packets or bottle caps, biting fingernails and chewing pens place concentrated force on the edges of veneers and should be avoided.
Grinding and clenching are a major threat, especially during sleep, when the forces are strongest and the person is unaware of them. People who grind their teeth are advised to wear a nightguard as recommended by their dentist. Grinding and its causes are discussed in the article on bruxism.
Staining foods and drinks, such as coffee, tea, red wine, curry and soy sauce, affect composite veneers more than ceramic ones, and they can also stain the margins of any veneer. Rinsing with water after these foods limits the effect. Smoking stains veneer margins and the underlying tooth and increases the risk of gum recession.
Regular professional check-ups and cleanings allow the dentist to inspect margins, remove stains and deposits with non-abrasive polishers and catch early wear or separation. Radiographs may be taken periodically to check the teeth under the veneers.
Side Effects After Bonding
Laminate veneers are considered a safe and minimally invasive treatment, but a few side effects can occur, most of them mild and temporary. Tooth sensitivity to hot or cold food and drink can appear shortly after the veneers are bonded. It is usually related to light enamel preparation or to the bonding materials, and it typically settles on its own. A desensitising toothpaste and avoiding very hot or cold drinks for a few days can help. Sensitivity that persists or worsens is checked by the dentist.
Marginal staining is a slower change. Ceramic veneers themselves resist stains, but the margin where the veneer meets the natural enamel can darken over time, especially with coffee, red wine, tobacco or poor hygiene. Regular professional cleaning, a non-abrasive toothpaste and rinsing after staining foods reduce the problem. In more advanced cases the margin may be polished or the veneer replaced.
Mild gum soreness or irritation can follow bonding, caused by the procedure itself or by a veneer edge that sits very close to the gum. This usually resolves within days with gentle brushing and warm salt-water rinses. If it continues, the dentist may need to adjust or polish the margin.
Colour mismatch is a planning issue. If the veneer shade does not match the surrounding teeth, the difference is noticeable. Very thin laminates placed over severely discoloured teeth can also let the dark colour show through, giving a greyish tone. Careful shade matching, try-in pastes and, where needed, whitening of the natural teeth before treatment help avoid this. In some heavily discoloured teeth, a slightly thicker conventional veneer is chosen so that the colour can be masked.
With careful planning, sound bonding technique and regular follow-up, most of these side effects are minor and manageable.
Reversibility, Full Crowns and Removal
Whether laminate veneers can be reversed depends on how much enamel was altered. When true no-prep veneers are bonded to untouched enamel, they can sometimes be removed later with limited consequences for the tooth. Even with minimal-prep veneers, however, the enamel is usually etched or lightly roughened, and removing a bonded veneer leaves traces of bonding material that have to be polished away. In most cases the tooth will then need a new veneer or another covering, and a return to completely untreated teeth is rarely possible. Patients are therefore encouraged to ask before treatment whether their plan involves no-prep or minimal-prep techniques and what removal would involve in the future.
Laminates also need to be distinguished from full-coverage crowns, a difference that often gets lost in media coverage of cosmetic dental treatment abroad. Images that show front teeth reduced to small stubs describe preparation for full crowns, where the tooth is reduced on every side. That reduction cannot be undone, and it changes the long-term outlook of the teeth. Laminate veneers work in the opposite direction. They are bonded to largely intact enamel and are chosen precisely to avoid that level of reduction.
Laminates look bulky only when they are poorly designed or poorly fitted. Made to the right thickness and bonded to a surface prepared as the plan requires, they mimic the translucency of natural enamel. A bulky look usually points to a veneer that is too thick for the space, a tooth that was not reshaped where it needed to be, or excess cement at the margins. The digital preview and the mock-up during planning are the stages where this is prevented, since the planned thickness and shape can be checked in the mouth before any veneer is made.
Treatment Time in Istanbul and What Drives the Cost
Laminate veneer names the technique, not the material: the same thin bonded layer can be made in composite resin or in ceramic, so a treatment plan should state which material is included. Composite laminate veneers are generally completed in one appointment because the dentist shapes the material directly on the tooth. Ceramic veneers need design, preparation, laboratory production, try-in and bonding appointments. For international patients, ceramic veneer treatment at Mosdent is typically organised within a five to seven day visit, depending on the case and the laboratory schedule. How such a visit is planned is described on our patient journey page.
The cost depends on the material, the number of teeth, the complexity of the design and whether composite or laboratory-made ceramic is chosen. It can also reflect scans, photography, mock-ups, temporary protection, laboratory work, bite adjustments and follow-up appointments. A written plan should state which teeth receive veneers, which may need crowns or preliminary care and what aftercare is included. Starting prices are listed on our price list, and the dentists at Mosdent confirm which items apply after the examination.
Examination Before Choosing Laminate Veneers
The decision to use laminate veneers is made after an examination that looks at the teeth, the gums, the bite and the smile together. The dentist checks the condition and thickness of the enamel, looks for decay and old fillings on the surfaces to be covered and examines the gums for inflammation or recession. Radiographs show the health of the roots and the bone. The bite is assessed for grinding wear, deep overlap of the front teeth and contacts that would put load on the veneers.
The patient's goals are discussed in concrete terms. The questions include how much the colour should change, whether the aim is to close gaps, lengthen short teeth or even out edges, and how many teeth show in a full smile. Photographs and a digital scan allow the proposed result to be previewed, and a mock-up can show the planned shape in the mouth before any tooth is touched.
Laminate veneers are one part of aesthetic dentistry, and they are often combined with other treatments. Whitening may be done first to set the base shade, gum contouring may be used to even the gum line, and orthodontic alignment may be recommended where teeth are too far out of position for veneers alone. When several of these steps are combined, the plan becomes a wider smile makeover, and the order of treatment is set so that each step prepares the ground for the next.
With these findings in hand, the options can be compared honestly. For healthy teeth with enough enamel and a stable bite, laminate veneers can change the appearance of the smile while keeping most of the natural tooth. Where the enamel, bite or tooth position does not allow that, conventional veneers, crowns or orthodontic treatment may achieve the goal more reliably, and the examination makes that choice clear.
Let’s plan the right treatment together.
Free Assessment→- 1.Klein P, Spitznagel FA, Zembic A, Prott LS, Pieralli S, Bongaerts B, et al. Survival and Complication Rates of Feldspathic, Leucite-Reinforced, Lithium Disilicate and Zirconia Ceramic Laminate Veneers: A Systematic Review and Meta-Analysis. J Esthet Restor Dent 2025;37:601-619. PubMed 39523553
- 2.Morimoto S, Albanesi RB, Sesma N, Agra CM, Braga MM. Main Clinical Outcomes of Feldspathic Porcelain and Glass-Ceramic Laminate Veneers: A Systematic Review and Meta-Analysis of Survival and Complication Rates. Int J Prosthodont 2016;29:38-49. PubMed 26757327
- 3.Gresnigt MM, Kalk W, Ozcan M. Randomized clinical trial of indirect resin composite and ceramic veneers: up to 3-year follow-up. J Adhes Dent 2013;15:181-90. PubMed 23534025
- 4.Gurel G, Sesma N, Calamita MA, Coachman C, Morimoto S. Influence of enamel preservation on failure rates of porcelain laminate veneers. Int J Periodontics Restorative Dent 2013;33:31-9. PubMed 23342345
- 5.Aslan YU, Uludamar A, Özkan Y. Clinical performance of pressable glass-ceramic veneers after 5, 10, 15, and 20 years: A retrospective case series study. J Esthet Restor Dent 2019;31:415-422. PubMed 31168916
- 6.Lim TW, Tan SK, Li KY, Burrow MF. SURVIVAL AND COMPLICATION RATES OF RESIN COMPOSITE LAMINATE VENEERS: A SYSTEMATIC REVIEW AND META-ANALYSIS. J Evid Based Dent Pract 2023;23:101911. PubMed 38035903
- 7.Edelhoff D, Sorensen JA. Tooth structure removal associated with various preparation designs for anterior teeth. J Prosthet Dent 2002;87:503-9. PubMed 12070513
- 8.Doughty J, Moore D, Ellis M, Jago J, Ananth P, Montasem A, et al. Contemporary dental tourism: a review of reporting in the UK news media. Br Dent J 2025;238:230-237. PubMed 40021870
- 9.Ghazanfari R, Azimi N, Nokhbatolfoghahaei H, Alikhasi M. Laser Aided Ceramic Restoration Removal: A Comprehensive Review. J Lasers Med Sci 2019;10:86-91. PubMed 31360375
- 10.Öztürk E, Bolay S. Survival of porcelain laminate veneers with different degrees of dentin exposure: 2-year clinical results. J Adhes Dent 2014;16:481-9. PubMed 25279393