Transnasal and subperiosteal implants are fourth-tier options for patients whose jaw can no longer anchor standard, tilted, zygomatic or pterygoid fixtures. A subperiosteal implant is a custom titanium framework laid on the bone surface beneath the periosteum, while a transnasal implant takes anchorage from the nasal floor and anterior nasal spine. A systematic review of 13 studies covering 227 patients and 227 additively manufactured subperiosteal implants found 97.8% still in function after a mean 21.4 months, with 25.6% showing partial exposure of the framework (PubMed 38315326). Candidacy is settled by CBCT measurement, not by clinical impression.
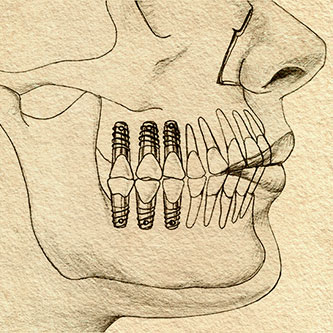
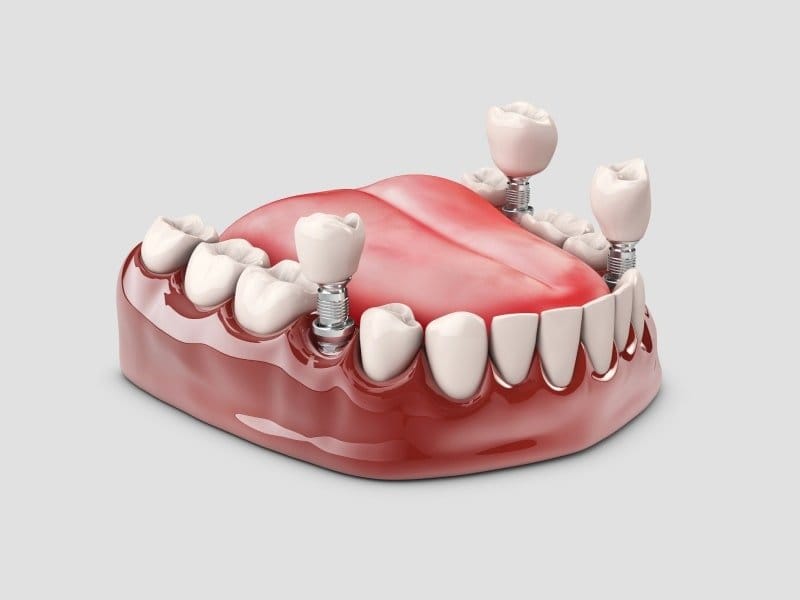
- 01A subperiosteal implant never enters the bone: a CAD-designed titanium framework rests on the jawbone under the periosteum and posts pass through the gum to carry the prosthesis.
- 02Short-term survival is documented but follow-up is short. Across 227 modern subperiosteal implants, 97.8% were in function at a mean 21.4 months, with 25.6% partial exposure and soft-tissue or persistent infection in 5.3% of patients (PubMed 38315326).
- 03Mandibular data sit separately: 40 additively manufactured frameworks in 19 patients with Cawood-Howell class IV to VII atrophy showed 92.5% survival after an average 804 days of follow-up (PubMed 40113460).
- 04Ten-year evidence exists but is thin. A single-centre series of 10 laser-sintered maxillary frameworks reported a Kaplan-Meier 10-year survival probability of 80%, with prosthetic loading deliberately delayed about five months (PubMed 40399182).
- 05Transnasal anchorage rests mainly on case reports and simulation. In a finite element study using a 150 N vertical load, the transnasal plus zygomatic model carried the highest implant stress, and adding pterygoid implants lowered it (PubMed 41344545).
Where These Implants Sit Among the Options
Transnasal and subperiosteal implants are needed when the jaw can no longer anchor the implant types that come before them: standard posts, tilted or short implants, and zygomatic or pterygoid implants. Most patients looking into implants will not come across these two terms. They come after the first three levels of treatment and serve a small group of patients for whom the other pathways have been used up or ruled out by anatomy or health.
If you have been told that standard implants are impossible, that zygomatic or pterygoid implants do not suit your anatomy, or that your bone loss is too severe for conventional approaches, these are the options that remain to be assessed. That assessment is a measured decision based on three-dimensional imaging, and it can still end with the conclusion that another route is safer.
At Mosdent in Istanbul, the team works with patients who arrive having been turned away elsewhere. Understanding the full range of implant solutions, including those at the far edge of current practice, is part of how a path forward is found for patients who thought one no longer existed.
The evidence for these two approaches is also younger and thinner than for standard implants, and that is part of the decision. A subperiosteal framework has pooled results reaching only a mean of just under two years, with a few longer series, and transnasal anchorage rests mainly on case reports and computer simulation. A patient choosing either one is choosing a treatment with promising early results, and it is fair to weigh that alongside the benefit of fixed teeth for someone who has no other fixed option. The sections below explain where each option sits, how each is built, what the published data show and how candidacy is decided.
The Four Levels of Implant Treatment
Implant options can be arranged in levels, and a patient moves to the next level only when the previous one cannot work. The order follows anatomy, not preference.
The first level is standard dental implants placed directly into the jawbone. They suit most implant patients and are often combined with bone grafting where bone volume is borderline. The second level uses angled or short implants. Tilted placement, as in All-on-4 and All-on-6 protocols, increases contact with the available bone, short implants are used where height is limited, and a sinus lift can add bone in the back of the upper jaw.
The third level is zygomatic and pterygoid implants. They anchor in the cheekbone or in the pterygoid plate at the back of the upper jaw, bypassing the resorbed ridge and reducing or removing the need for grafting. A four-implant zygomatic protocol, known as quad zygoma, is used where conventional implants cannot be placed in the front of the upper jaw, and a case report on the severely atrophic upper jaw notes that the technique has some difficulties and needs surgical experience (PubMed 37982810).
The fourth level is transnasal and subperiosteal implants. They are reserved for cases where none of the above is anatomically viable, or where the patient's health makes the earlier options unreliable. They work with the bone that remains: the bone surface under the gum, or the dense bone at the floor of the nose and the anterior nasal spine.
For most patients, the first three levels give good outcomes. The fourth level exists for extreme bone loss, complex anatomy, repeated failed grafts or certain systemic conditions, where it may be the remaining pathway to fixed teeth.
How a Subperiosteal Implant Is Built and Held
A subperiosteal implant does not enter the bone. It is a custom framework laid on the surface of the jawbone, beneath the periosteum, the dense connective tissue layer that covers bone. Posts from the framework pass through the gum and carry the prosthesis.
The concept is old. Early subperiosteal implants were made from impressions of the bone and cast in metal, and their results varied because the fit was imprecise. The modern version is designed from CBCT data with CAD software and produced by additive manufacturing, typically in titanium, so the framework matches the scanned bone surface closely. The periosteum is lifted during surgery, the framework is seated and fixed with screws in areas where the bone is thick enough, and the tissue is closed over it. The fit of the framework and the fixation screws hold it in place while the soft tissue heals around it.
Indications follow from how it works. A subperiosteal implant is considered when the ridge has resorbed to a thin or flat form that cannot hold any post, when zygomatic and pterygoid implants are not feasible, when several bone grafts have already failed, or in certain defects after surgery or trauma. Systemic conditions can also point this way. In severe osteoporosis or specific bone metabolic disorders, grafting can be unreliable, and a framework that rests on the bone surface may be discussed as an option, although patients taking bisphosphonates need specific evaluation because of the risk of medication-related osteonecrosis of the jaw.
The step that decides success is the three-dimensional assessment of the remaining bone surface. The framework is only as good as the scan and the design it is built from, which is why this treatment is planned digitally from start to finish.
Published Results for Modern Subperiosteal Implants
The short-term data for modern subperiosteal implants are encouraging, and the follow-up is still short. A systematic review of 13 articles, five cohort studies and eight case series, covered 227 patients and 227 additively manufactured implants. After a weighted mean follow-up of 21.4 months, 97.8 percent of implants were in function (PubMed 38315326).
The same review showed where problems arise. Partial exposure of the framework occurred in 58 implants, or 25.6 percent, and 12 patients, or 5.3 percent, had soft tissue or persistent infection (PubMed 38315326). Fracture of the interim prosthesis was reported in 8 of the 155 patients in whom a provisional prosthesis was used, which is 5.2 percent (PubMed 38315326). The authors could not pool the results in a meta-analysis because the studies differed too much in design.
Lower-jaw data sit in a separate series. A multicentre retrospective study of 40 additively manufactured frameworks in 19 patients with severe mandibular atrophy, Cawood-Howell classes IV to VII, reported survival of 92.5 percent after an average follow-up of 804 days (PubMed 40113460). Mucosal recession was noted around 13 implants, 32.25 percent, but patients did not regard it as a functional or aesthetic concern (PubMed 40113460).
The longest follow-up comes from a small upper-jaw series. Ten patients received 10 laser-sintered frameworks, eight remained functional and two were removed because of inadequate fit and recurrent infection, giving a Kaplan-Meier 10-year survival probability of 80 percent (PubMed 40399182). With so few patients, that figure is an early signal of how long frameworks can last. Any longevity figure you are given should be read together with the follow-up period and the number of patients behind it.
How a Transnasal Implant Finds Bone
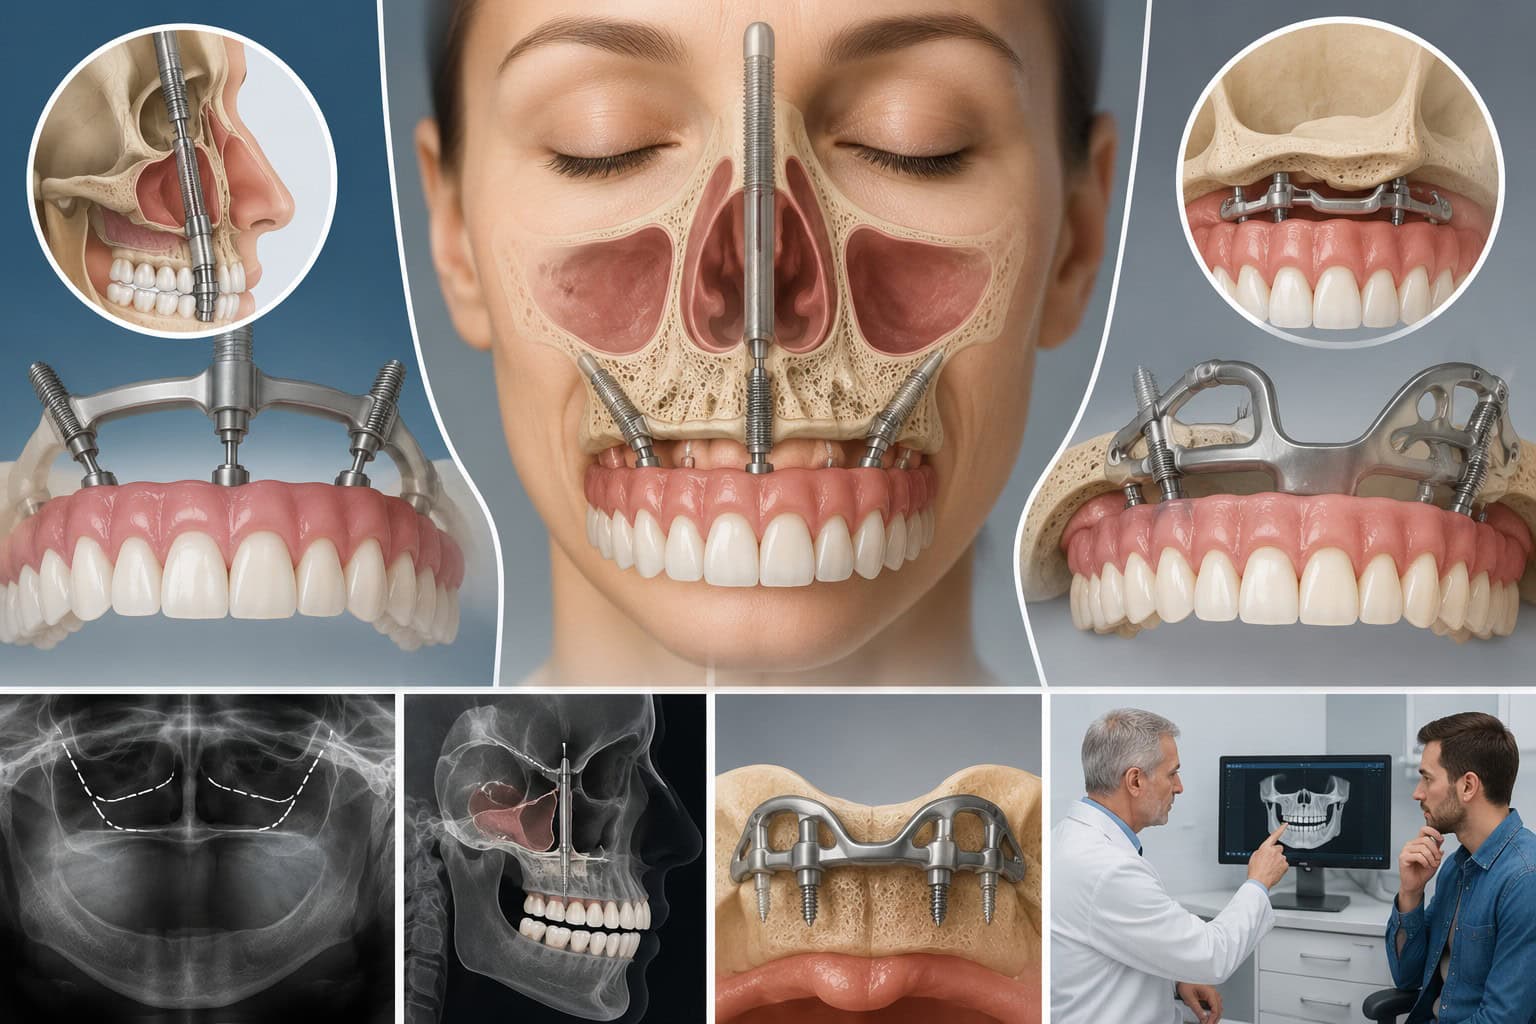
A transnasal implant takes its anchorage from the bone at the floor of the nasal cavity and the anterior nasal spine, reaching it through a planned path in the front of the upper jaw. It is used when the ridge above the front teeth has resorbed so far that no standard implant can be placed there, even with grafting.
The anatomical reasoning is that the bone forming the nasal floor, the nasal process of the upper jaw and the anterior nasal spine often keeps more density and volume than the alveolar ridge in patients with advanced bone loss. A carefully planned transnasal path gives the implant access to that bone, which standard placement in the front of the jaw cannot reach.
A transnasal implant is different from a zygomatic implant. A zygomatic implant anchors in the cheekbone and supports the back of the upper jaw, while a transnasal implant anchors at the nasal floor and supports the front. The two address different regions of bone loss and are often combined.
Candidates share a recognisable pattern. The front of the upper jaw has lost so much bone that standard implants cannot be placed there, the nasal floor bone remains intact and accessible, and a full-arch restoration needs support at the front where no other anchorage is available. In many plans transnasal implants are combined with zygomatic or pterygoid implants to complete the arch.
This pathway lies close to the lining of the nasal cavity and other structures, so it is not suitable for every patient with front bone loss. It depends on precise three-dimensional planning and on surgical experience in this region. Mosdent's oral and maxillofacial surgery team analyses the imaging in detail to judge whether the pathway is viable and safe for the individual patient.
Evidence Behind Transnasal Anchorage
Transnasal anchorage is supported mainly by case reports and by computer simulation, and it has no long-term clinical series comparable to those for standard implants. A patient considering it should know that the evidence describes how the approach can work mechanically and in selected cases, and that long-term survival figures are not yet available.
A case report on the severely atrophic upper jaw describes the reasoning behind it. Grafting to rebuild such a jaw has drawbacks, including long treatment, major surgery and morbidity at the donor site, and quad zygoma is one alternative, with transnasal implants combined with zygomatic implants, and subperiosteal implants, as further alternatives; the report presents a patient treated with zygomatic, pterygoid and transnasal implants together (PubMed 37982810).
A finite element study modelled three designs in the atrophic upper jaw under a vertical load of 150 N. The first combined transnasal and zygomatic implants, the second used four zygomatic implants, and the third added pterygoid implants to the transnasal and zygomatic combination. The highest stress on the implants appeared in the first model, and the lowest stress on implants, abutments and bone appeared in the third (PubMed 41344545). The authors concluded that transnasal with zygomatic implants may serve as an alternative to quad zygoma, and that adding pterygoid implants may bring a further biomechanical advantage (PubMed 41344545).
A simulation shows how load is shared in a model; it does not show how patients fare over years. What it supports is the planning logic seen in practice, where transnasal implants are rarely placed alone and are usually part of a combined design with anchorage at several sites.
CBCT Planning Before Any Recommendation
For a standard implant, a panoramic X-ray and clinical examination may be enough to plan. For the cases described here, cone beam computed tomography, known as CBCT, is required before any recommendation is made. The difference between a zygomatic implant being viable and a subperiosteal framework being required is settled by measurement, and a clinical impression cannot replace it.
CBCT provides several measurements at once. It shows the remaining bone volume at every possible anchorage site in millimetres, maps the shape of the bone surface that a subperiosteal framework must match, and shows the transnasal path in relation to the nasal cavity, the floor of the orbit and neighbouring structures. On the same data the implant positions can be simulated digitally before surgery, and anatomical reasons not to proceed can be identified before the patient reaches the operating room.
At Mosdent, every complex implant assessment begins with CBCT imaging and digital treatment planning, and the surgical team reviews the three-dimensional data before any surgical recommendation is made.
If you already have scans from another clinic, bring them. They can show how the bone has changed over time, and they help the team understand why earlier plans were ruled out. Being told that standard implants are impossible describes one level of the treatment hierarchy, and the useful next step is fresh three-dimensional imaging reviewed by a team that works with all four levels. That review may confirm a fourth-level option, point back to a zygomatic or pterygoid plan that was not considered, or show that grafting is still possible. Each of those outcomes is more useful than a second opinion on the same radiograph.
Gum Treatment and General Health Before Surgery
Patients who need subperiosteal or transnasal implants have usually lost a great deal of bone, and in many of them that loss was driven or accelerated by periodontal disease. Before any advanced implant procedure, the soft tissue must be assessed and, where needed, treated.
Active gum disease creates a bacterial environment that raises the risk of complications around implants, including those that rest on the bone surface. The published subperiosteal data show that most reported problems concern the soft tissue: exposure of the framework and infection. A framework placed under inflamed tissue starts at a disadvantage, whatever its design.
Mosdent's periodontology team assesses every complex implant candidate before surgery. Where disease is active, gum surgery or periodontal flap surgery is completed first, alongside non-surgical treatment, so that the implant is placed into a stable soft tissue environment.
General health also shapes which option is chosen. In severe osteoporosis, bone density may be too low for reliable integration even where bone volume looks adequate. After radiotherapy to the jaw, irradiated bone heals poorly, and anchorage in bone outside the radiation field, such as the cheekbone, may be considered. After two or more failed grafts, further grafting is often a poor choice and options that avoid it become more attractive. Uncontrolled systemic disease needs to be managed before surgery of this complexity. For patients with complex medical histories, the team coordinates with the relevant medical specialists before the plan is finalised.
Surgery, Recovery and Loading of the Final Teeth
At Mosdent, subperiosteal and transnasal procedures are performed under general anaesthesia or deep sedation, managed by the anaesthesia team. Published practice varies with the case: in one upper-jaw subperiosteal series, a limited number of fixation screws, 7 to 10, placed only where bone was thick enough allowed the procedures to be done under local anaesthesia in an outpatient setting (PubMed 40399182). The choice depends on the extent of surgery and the patient's health.
Recovery is more involved than after a standard implant, but it follows the same principles. In the first few days, swelling, bruising and discomfort are expected, and cold compresses, prescribed pain relief and antibiotics manage this phase; keeping the head raised during rest reduces swelling. In a mandibular series, the most common early events were oedema and temporary infection, generally managed with chlorhexidine mouth rinses, antibiotics and paracetamol (PubMed 40113460). In the following weeks a soft diet, limited physical activity and careful cleaning around the points where the posts emerge are advised, and after transnasal surgery forceful nose blowing is avoided.
The timing of fixed teeth is decided case by case. In some cases a provisional fixed prosthesis is attached at surgery, depending on the stability achieved. In others loading is deliberately delayed. The ten-patient upper-jaw series delayed prosthetic loading by approximately five months because of the reduced number of fixation points and the compromised anatomy (PubMed 40399182). Ask what your surgical plan assumes before booking travel, since the answer changes how many trips you need.
Recovery instructions are given in writing before treatment, and international patients receive a protocol for managing recovery during their stay and after they return home.
Completing the Smile and Arranging an Assessment
Once subperiosteal or transnasal treatment is complete and the definitive prosthesis is in place, many patients turn to aesthetic treatments they have not been able to consider for years. These are planned around the new arch so that the result reads as one.
A smile makeover coordinates the full-arch restoration with broader aesthetic goals, and Hollywood smile design extends that to the visible teeth in both arches. Pink dental aesthetics shapes the gum to frame the new restoration. Where natural teeth remain in the opposing arch, teeth whitening brings them closer to the prosthetic shade, and zirconium crowns can restore those teeth so that both arches match.
The phrase that you do not have enough bone for implants describes the anatomy at one level of the treatment hierarchy, and the hierarchy extends further than many patients are told. Subperiosteal and transnasal implants sit at the edge of what implant dentistry currently offers. They are demanding procedures with a short evidence base, and for the right patient they can provide fixed teeth where earlier plans found no way.
If you have been through several consultations without a clear plan, Mosdent invites you to bring your imaging and history for review. The oral and maxillofacial surgery team, working within Mosdent's wider implant service, will go through every option available to you, including those you may not have heard of, and explain the evidence behind each. Contact us to arrange an assessment.
Let's plan the right treatment together.
Free Assessment→- 1.Anitua E, Eguia A, Staudigl C, Alkhraisat MH. Clinical performance of additively manufactured subperiosteal implants: a systematic review. Int J Implant Dent 2024;10:4. PubMed 38315326
- 2.Van den Borre C, Otero JJ, Loomans N, Samama M, Lempert J, Baltensperger M, et al. Retrospective analyses of additively manufactured subperiosteal jaw implants in the mandible. J Craniomaxillofac Surg 2025;53:905-910. PubMed 40113460
- 3.Łoginoff J, Majos A, Elgalal M. Long-term clinical results of additively manufactured subperiosteal implants for the treatment of the severely atrophic maxilla. J Craniomaxillofac Surg 2025;53:1283-1290. PubMed 40399182
- 4.Togac E, Ayranci F, Tapci O. Finite element analysis of transnasal, zygomatic and pterygoid implants in the rehabilitation of the atrophic maxilla. J Stomatol Oral Maxillofac Surg 2026;127:102674. PubMed 41344545
- 5.Şahin O. Treatment of Severely Atrophic Maxilla by Using Zygomatic, Pterygoid, and Transnasal Implants. J Craniofac Surg 2024;35:e145-e146. PubMed 37982810