Replacing an old crown or veneer means removing the existing restoration, reassessing the tooth beneath it for decay and marginal integrity, and fabricating a new one in a current material. Age alone is not the trigger; a dark line at the gumline, chipped porcelain, persistent sensitivity or a crown that moves are. In a retrospective cohort of 255 posterior crowns in 235 patients, ten-year cumulative survival was 86.0% for monolithic zirconia against 71.0% for porcelain-fused zirconia (PubMed 39984403). At five years, a 64-study meta-analysis put metal-ceramic single crowns at 97.1% and monolithic zirconia at 96.8% (PubMed 41489982).
- 01Renewal is a reassessment, not a swap: the tooth under an old crown is examined for secondary decay and marginal gaps before any new restoration is designed.
- 02Ten-year cumulative survival diverged by design in 255 posterior crowns: 86.0% for monolithic zirconia and 71.0% for porcelain-fused zirconia (PubMed 39984403).
- 03The same cohort identified two risk factors for crown complications: a molar rather than premolar position (hazard ratio 6.012) and a maxillary rather than mandibular crown (hazard ratio 9.487) (PubMed 39984403).
- 04Across 64 studies covering 3,509 metal-ceramic and 8,051 all-ceramic single crowns, monolithic designs showed significantly fewer ceramic fractures and chipping than veneered alternatives, and feldspathic ceramic trailed at 90.4% five-year survival (PubMed 41489982).
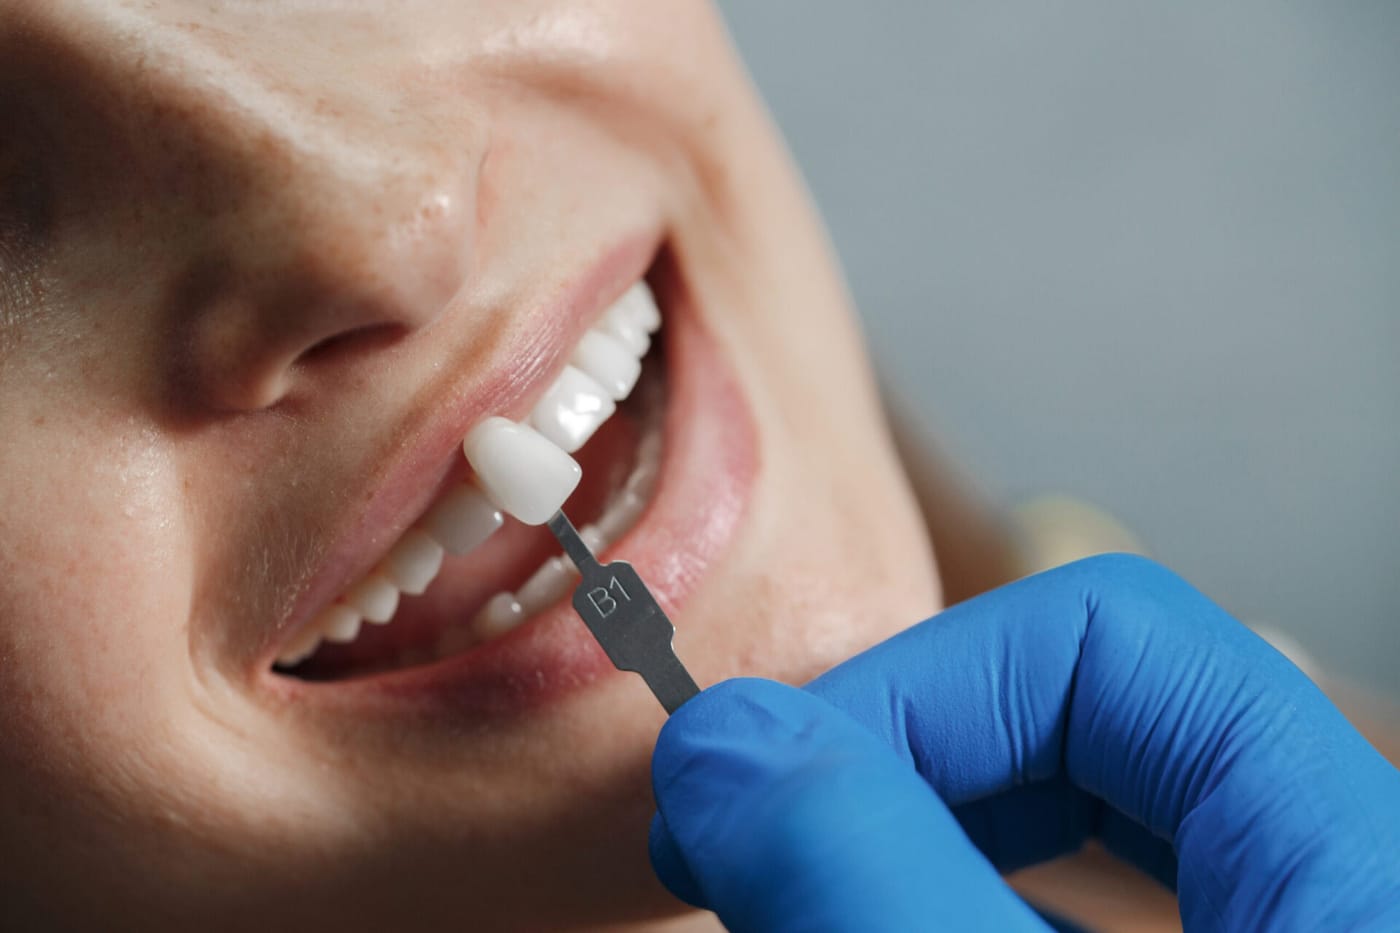
- 05Shade matching is the technical limit in partial renewals: ceramic does not bleach, so whitening of remaining natural teeth is completed before the new shade is chosen.
There is a specific moment that many people with older dental restorations experience, usually when looking at a photograph rather than a mirror. The crowns that seemed perfectly acceptable for years suddenly look grey, opaque, or noticeably different from the surrounding teeth. The veneers that were placed a decade ago have a slightly yellowish tint or a visible dark line at the gumline. The smile that was once an improvement has become, almost imperceptibly, something that draws the eye for the wrong reasons.
Old dental crowns and veneers do not fail catastrophically overnight. They age and their aging becomes visible gradually, then all at once.
The good news is that replacing aging restorations with modern materials is one of the most rewarding procedures in cosmetic dentistry. The difference between a set of porcelain-fused-to-metal crowns from the early 2000s and a set of high-translucency zirconia restorations produced today is substantial. At Mosdent Dental Hospital in Istanbul, part of the caseload is patients who travel for this reason alone, to replace aging dental work with current materials.
/ Aesthetic Signs That Your Old Crowns or Veneers Need Replacing
Not every old restoration needs immediate replacement. Some crowns and veneers placed decades ago continue to function well while others have failed structurally, aesthetically, or both. Knowing which category your restorations fall into is the starting point.
Aesthetic Indicators
Dark or grey appearance: This is the most common complaint about older porcelain-fused-to-metal (PFM) crowns. The metal substructure absorbs and blocks light rather than transmitting it, giving the tooth an opaque, grey quality compared to surrounding natural teeth. Under certain lighting, especially in photographs, the difference becomes stark.
Visible dark line at the gumline: As gum tissue naturally recedes over the years, the metal margin of a PFM crown becomes progressively more visible. This dark line at the gumline is one of the most telltale signs of an aging metal-ceramic restoration and it worsens with time, not improves.
Yellowing or surface staining: Porcelain can develop micro-surface changes over many years that make it more susceptible to staining. Veneers placed ten or more years ago may have lost some of their original brightness.
Unnatural appearance: Older ceramic techniques produced restorations that, compared to today's high-translucency options, can look flat, opaque, or uniformly bright, lacking the natural gradients and depth of contemporary restorations.
Chipped or cracked porcelain: A common issue with PFM crowns, where the porcelain layer chips away from the metal substructure. Small chips may be repairable, but multiple chips or an extensive fracture typically warrants full replacement.
/ Functional Signs and Lifespan Expectations for Old Crowns and Veneers
Functional signs and restoration lifespan help determine whether old crowns or veneers need replacement.
Functional and Structural Indicators
Sensitivity or pain around an old crown: Persistent sensitivity can indicate secondary decay forming beneath the crown, failed marginal seal, or root canal issues in the underlying tooth.
Looseness or movement: A crown that rocks or moves slightly is no longer properly sealed, bacteria have entered the marginal gap, and structural failure is likely imminent.
Recurring gum irritation around a specific restoration: Chronic inflammation around a particular crown is often caused by a marginal defect, an ill-fitting contour, or material incompatibility.
A crown or veneer that has partially come off: This is an obvious structural failure requiring immediate attention.
Old restorations on teeth that now require root canal treatment: A previously crowned tooth that subsequently develops infection will require removal of the existing crown to access the root canal system, followed by a new crown after treatment.
How Long Should Dental Crowns and Veneers Last?
Understanding realistic lifespans helps frame the replacement decision.
Porcelain-fused-to-metal (PFM) crowns: Historically the most common type, PFM crowns are mostly replaced for aesthetics (dark margin, porcelain chipping) or marginal failure. After 20 years, 78.8% of posterior metal-ceramic single crowns survived, with frequent veneering ceramic defects (PubMed 30209575).
Full porcelain and early all-ceramic crowns: Variable lifespan depending on the ceramic system used. Older all-ceramic systems had higher fracture rates in posterior positions; more recent formulations perform significantly better.
Zirconium crowns : Across 64 studies, monolithic zirconia crowns reached 96.8% five-year survival (PubMed 41489982).
Porcelain veneers : Well-placed veneers hold up well: 87% of 413 pressed lithium disilicate veneers survived 20 years (PubMed 31168916). Lifespan is affected by oral hygiene, grinding habits, and the health of the underlying tooth.
Laminate veneers : Similar lifespan to porcelain veneers; the minimal preparation involved means replacement is also less invasive.
Emax crowns and veneers : Well-documented 10-year survival rates above 90% in anterior positions. The material ages gracefully without the grey margin issues of metal-ceramic restorations.
/ Replacing Old PFM Crowns and Veneers
The process varies depending on what type of restoration is being replaced and what it is being replaced with. Here is what to expect across the main scenarios.
Replacing Old PFM Crowns with Zirconium
This is the most common renewal case we see at Mosdent: patients with PFM crowns from one or two decades ago seeking the aesthetic and functional upgrade that modern zirconium provides.
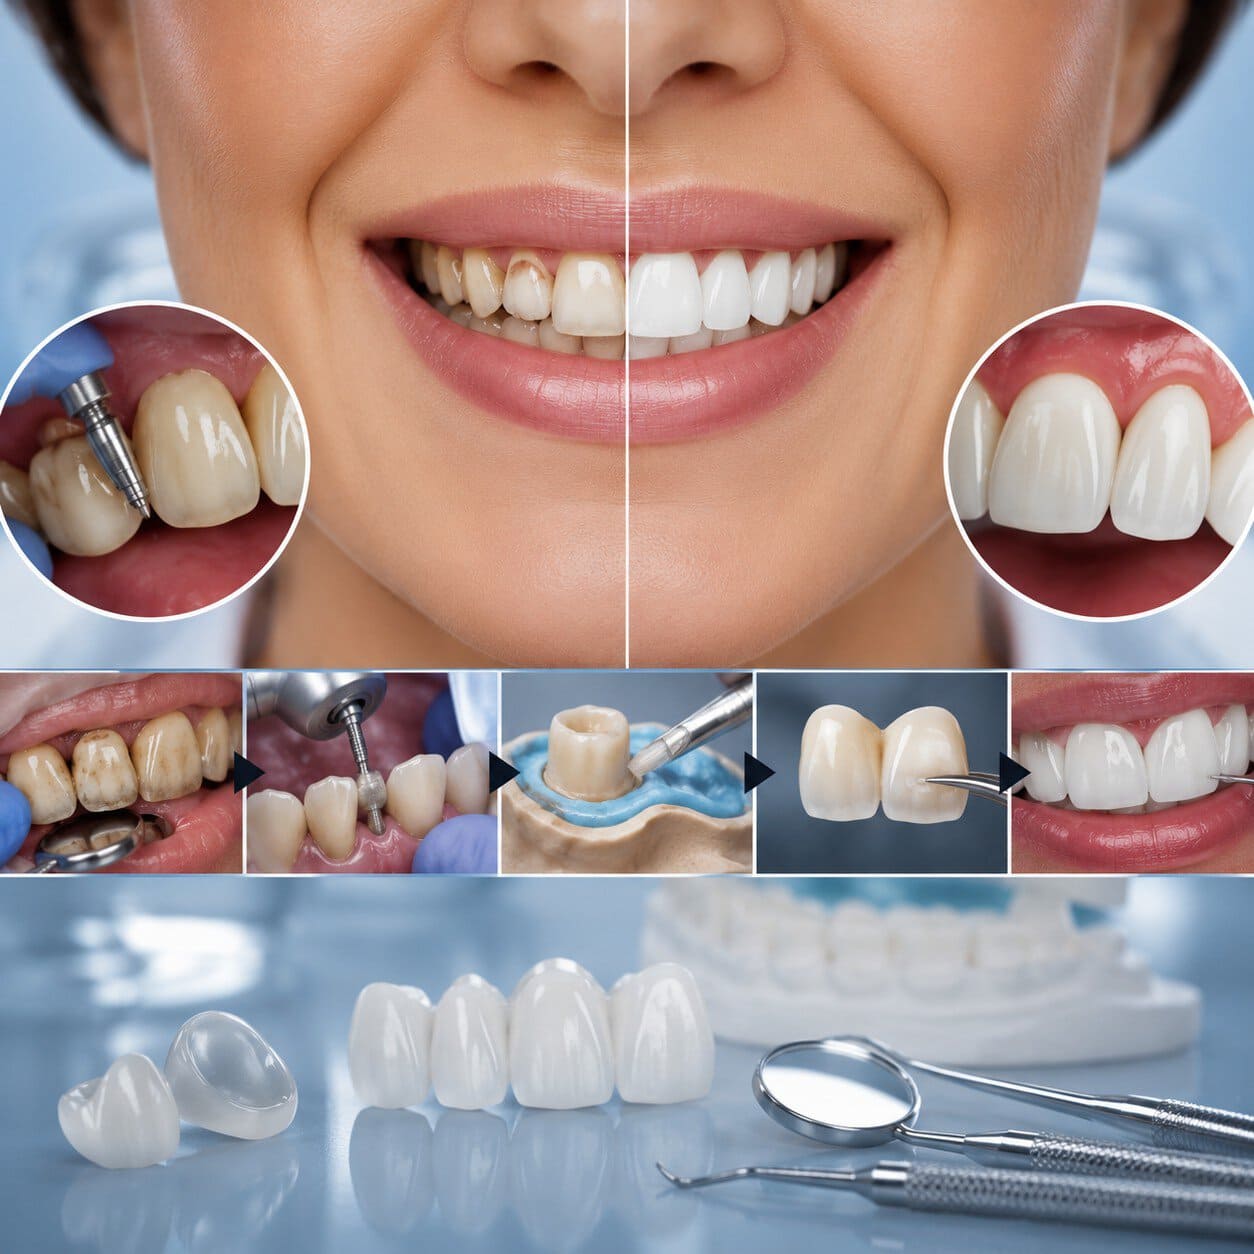
The process: The existing crown is carefully removed using specialised instruments. The underlying tooth is assessed, for decay, root integrity, and remaining tooth structure. If the preparation remains adequate, impressions (now increasingly done digitally) are taken and a new zirconium crown is designed and fabricated.
What to expect: A marked improvement in natural appearance. No dark margin. Better light transmission. Improved marginal fit due to CAD/CAM precision. Longer expected service life.
Important consideration: If the tooth beneath the old crown has developed secondary decay, that must be treated before the new crown is placed. If significant decay has compromised tooth structure, post and core build-up may be required first. A thorough assessment after crown removal establishes exactly what is needed.
Replacing Old Veneers
Veneer replacement is generally less invasive than crown replacement, as the preparation under a veneer is shallower. However, the existing veneer must be carefully removed without damaging the prepared tooth surface beneath.
When replacement is worthwhile: When the existing veneer shows staining, chipping, gingival recession revealing the margin, or a noticeable difference in shade from adjacent teeth or newer restorations. If the rest of the smile is being updated with new restorations, maintaining old veneers alongside creates an inevitable mismatch.
Material upgrade options: Older feldspathic porcelain veneers can be replaced with modern lithium disilicate ( Emax ) or prepless laminate options where tooth preparation allows.
/ Replacing Implant Crowns in Smile Renewal
Replacing Crowns on Implants
Implant crowns, like natural tooth crowns, have a finite lifespan. The implant usually outlasts the crown on top: across 46 studies, implants supporting single crowns survived at 95.2% after 10 years while the crowns themselves survived at 89.4%, with technical and aesthetic complications frequent (PubMed 23062124).
Replacing an implant crown is generally straightforward: the crown is unscrewed or carefully removed, and a new zirconium crown is fabricated and replaced. The implant connection is typically unaffected.
Comprehensive Smile Renewal
Many patients use the opportunity of replacing one or two failing restorations as a starting point for a broader smile makeover . When multiple restorations of varying ages are present, such as some original PFM crowns, some veneers and some more recent work, achieving a unified, consistent aesthetic outcome across the whole smile is far more satisfying than addressing individual restorations piecemeal.
A comprehensive smile renewal plan at Mosdent coordinates shade selection, shape design, and material choice across all restorations to create a cohesive result rather than a patchwork of different materials and ages.
The Role of Gum Health in Restoration Renewal
This is a step that is frequently underestimated, particularly in patients replacing old work.
Old PFM crowns with metal margins often sit in a local gum environment that has been chronically irritated for years, with low-grade inflammation, slight recession, and tissue changes that have accumulated gradually. Before placing new restorations, this tissue environment must be assessed and stabilised.
Mosdent's periodontology team evaluates gum health before any restorative renewal. Where active gum disease is present, it is treated first. In cases where gum recontouring is desirable for aesthetic reasons, equalising gum levels across adjacent teeth or improving the gum-to-tooth proportion, pink dental aesthetics procedures are incorporated into the renewal plan.
A new crown placed on unhealthy gum tissue is a restoration built on an unstable foundation. The few additional steps required to establish tissue health before renewal dramatically improve both the aesthetic and functional longevity of the new restorations.
/ Hollywood Smile Updates and Shade Matching in Partial Renewals
For patients whose original Hollywood smile treatment was performed 10–15 or more years ago, a renewal visit offers the opportunity to benefit from everything that has changed in material science and digital fabrication since the original work.
The combination of high-translucency zirconium, Emax ceramics, digital smile design technology, and CAD/CAM precision manufacturing means that restorations available today are simply better in appearance, fit, longevity, and biological compatibility than what was available a decade ago.
Patients undergoing a full Hollywood smile renewal at Mosdent receive a digital preview of the updated result before any treatment begins, and the full treatment, from assessment through final cementation, is typically completable within a 7–10 day visit for international patients.
Shade Matching: The Critical Detail in Partial Renewals
When only some restorations are being replaced rather than all, shade matching between the new work and the remaining existing restorations and any natural teeth is the most technically demanding aspect of the case.
Digital shade analysis, shade mapping under multiple lighting conditions, and experienced ceramist collaboration are all part of achieving a result where the renewal is invisible, where no one can identify which restorations are new and which are original.
For patients combining restoration renewal with teeth whitening of remaining natural teeth, whitening should always be completed first, so the new restorations can be shade-matched to the final whitened colour rather than the pre-whitening baseline.
/ Frequently Asked Questions
Can old crowns be replaced without damaging the tooth underneath? In most cases, existing crowns are removed using specialised instruments that minimise the risk of damaging the underlying tooth. The tooth beneath is then assessed and any issues such as decay, marginal gaps or structural compromise are addressed before the new crown is placed.
How many appointments does crown or veneer replacement take?
For a limited number of restorations, typically two appointments: one for removal, assessment, and preparation; one for fitting the final restorations. International patients at Mosdent can usually complete this process within 5–7 days.
Will replacing my old crowns hurt?
The procedure is performed under local anaesthesia. Any sensitivity to the prepared teeth between appointments is managed with temporary restorations and resolves after final cementation.
Do I need to replace all my crowns at once?
Not necessarily. However, replacing all restorations in the smile zone simultaneously allows for consistent shade matching across the entire visible smile. Replacing individual crowns in isolation can result in visible shade differences between old and new restorations.
Is it worth replacing crowns that are still functional?
If the crowns are structurally sound but aesthetically outdated, the decision is elective. Many patients find the aesthetic improvement from updating PFM crowns to modern zirconium is substantial enough to warrant the investment even when the old crowns have not technically failed.
/ What Modern Materials Can Achieve That Older Restorations Cannot
A patient replacing 15-year-old PFM crowns with high-translucency zirconium is not simply getting newer versions of the same thing. They are accessing a fundamentally different category of aesthetic and functional outcome:
- Natural light transmission rather than opacity
- No metal margin visible now or in the future
- Marginal fit precision measured in microns rather than fractions of millimetres
- Full biocompatibility with zero risk of tissue irritation from metal
- Colour stability, since fired ceramic resists staining
- Measured survival: 96.8% at five years for monolithic zirconia crowns across 64 studies (PubMed 41489982)
At Mosdent Dental Hospital, our aesthetic dentistry team has guided patients through restoration renewal across every combination of material and clinical scenario. Whether you are updating a single crown or completing a full smile renewal, the starting point is a comprehensive assessment that establishes exactly what is present, what is needed, and what is achievable.
Explore our aesthetic dentistry services or contact our team to arrange a free consultation for your restoration renewal.
Let’s plan the right treatment together.
Free Assessment→- 1.Takaesu Y, Taniguchi Y, Kaga N, Yamaguchi Y, Kakura K, Suzuki N, et al. Long-term clinical outcomes of posterior monolithic and porcelain-fused zirconia crowns: A retrospective cohort study. J Prosthet Dent 2025;133:1475-1483. PubMed 39984403
- 2.Pjetursson BE, Pitta J, Balet A, Bjarnadottir GR, Sailer I, Romandini P. A Systematic Review and Meta-analysis Evaluating the Survival, Failure, and Complication Rates of Metal-Ceramic, Veneered, and Monolithic All-Ceramic Tooth-Supported Single Crowns-Part 1. Int J Prosthodont 2026;39:308-324. PubMed 41489982
- 3.Gurel G, Sesma N, Calamita MA, Coachman C, Morimoto S. Influence of enamel preservation on failure rates of porcelain laminate veneers. Int J Periodontics Restorative Dent 2013;33:31-9. PubMed 23342345
- 4.Reitemeier B, Hänsel K, Range U, Walter MH. Prospective study on metal ceramic crowns in private practice settings: 20-year results. Clin Oral Investig 2019;23:1823-1828. PubMed 30209575
- 5.Aslan YU, Uludamar A, Özkan Y. Clinical performance of pressable glass-ceramic veneers after 5, 10, 15, and 20 years: A retrospective case series study. J Esthet Restor Dent 2019;31:415-422. PubMed 31168916
- 6.Jung RE, Zembic A, Pjetursson BE, Zwahlen M, Thoma DS. Systematic review of the survival rate and the incidence of biological, technical, and aesthetic complications of single crowns on implants reported in longitudinal studies with a mean follow-up of 5 years. Clin Oral Implants Res 2012;23 Suppl 6:2-21. PubMed 23062124