A loose denture is usually a bone problem rather than an adhesive problem. After extraction the alveolar ridge resorbs: a systematic review of 20 human studies found horizontal bone loss of 29 to 63 percent and vertical loss of 11 to 22 percent within six months, with the fastest change in the first three to six months (PubMed 22211303). The denture keeps its original shape while the ridge beneath it flattens, so adhesive demand climbs. The real fixes are relining, a remade denture, an implant-retained overdenture, or a fixed implant-supported arch.
- 01Rising adhesive use is a fit signal, not a habit: the ridge that once supported the denture is resorbing while the prosthesis keeps the shape it was made in.
- 02The resorption is measured, not theoretical: 29 to 63 percent horizontal and 11 to 22 percent vertical bone loss at six months after extraction, across 20 human studies (PubMed 22211303).
- 03Relining replaces the inner fitting surface against the ridge as it is now, and is the right answer when the discrepancy is moderate and the denture is structurally sound.
- 04An implant-retained overdenture converts retention from suction to mechanical connection: in a randomized trial of 60 edentulous patients, general satisfaction with a two-implant mandibular overdenture ran about 36 percent higher than with a new conventional denture (PubMed 14651229).
- 05Adhesive cannot replace lost bone support, cannot slow resorption, and does not meaningfully raise chewing force on a poorly supported denture.
Rising Adhesive Use Signals a Fit Problem
A denture that needs more and more adhesive to stay in place is telling you that its fit has changed, and the fix lies in the fit itself. Many long-term denture wearers reach a point where the amount of adhesive needed to get through a meal has quietly doubled, where the lower denture shifts while they talk, and where certain foods have dropped off the menu because chewing them became unreliable. Each step feels small, so the change is easy to accept as part of wearing dentures.
Adhesive in this situation works as a patch over a gap that keeps widening. The looseness has specific causes that can be examined, and each cause has a matching clinical answer, from refitting the existing denture to a new denture, an implant-retained overdenture or a fixed implant-supported arch.
At Mosdent in Istanbul, we regularly see patients who have been managing worsening denture looseness with increasing amounts of adhesive for years before discovering that alternatives exist. The route out starts with understanding why the denture became loose, because the cause decides which option makes sense. A denture that is structurally sound on a ridge that has changed only a little needs a different answer from a ten-year-old denture on a ridge that has flattened, and both differ from the situation of someone who wants to stop removing their teeth altogether.
Bone Resorption Under the Denture
The main reason dentures loosen over time is that the jawbone beneath them shrinks. When a tooth is removed, the bone that held its root no longer receives the loading it needs to keep its volume, and the body gradually resorbs it. The process continues under a denture and stays largely invisible until the fit changes.
The size of this change has been measured. A systematic review of 20 human studies found horizontal bone loss of 29 to 63 percent and vertical bone loss of 11 to 22 percent 6 months after tooth extraction (PubMed 22211303). The same review reported rapid reductions in the first 3 to 6 months, followed by more gradual reductions afterwards (PubMed 22211303). The ridge is therefore changing fastest in the months right after extraction, and it keeps changing more slowly over the years of denture wear that follow.
The denture does not follow this change. It keeps the shape of the ridge it was made for, while the ridge under it becomes lower and narrower. The contact between the fitting surface and the gum shrinks, suction weakens and the denture begins to rock when you bite on one side. This is why a denture that fitted well when it was made can become loose without any fault in its manufacture or material. Adding adhesive fills part of the growing gap, but it does not restore the bone, and the gap keeps widening whether or not glue is used. A rising adhesive requirement is therefore a fairly direct reading of how far the ridge has moved away from the denture.
Saliva, Acrylic Wear and Soft Tissue Changes
Bone loss is the main driver, but three other changes add to it and can make a denture loose even when the ridge has changed only a little.
Saliva forms the thin film that creates suction between the denture and the gum, so less saliva means weaker retention. Dry mouth is common. A review in JAMA reported that in a meta-analysis of 26 population-based studies, the global prevalence of dry mouth symptoms was 23 percent (PubMed 38530258). The same review linked dry mouth to using more than 3 oral medications per day, as well as head and neck radiation and Sjögren disease (PubMed 38530258). Many denture wearers are older adults who take several medicines, so reduced saliva often arrives at the same time as ridge resorption.
The denture itself also ages. Acrylic can distort slightly over years of temperature changes, cleaning and chewing stress, and the teeth wear down. Even a denture that fitted well at the start can gradually lose its original fit geometry and its bite height, which changes how chewing forces push on it.
Finally, the soft tissues around the denture change. Weight loss, thinning of the gum covering the ridge and changes in the cheek and lip muscles with age all alter how a denture sits and how the muscles hold it in place. These factors matter for the choice of fix. Reduced saliva can be managed alongside any option, a worn denture points toward replacement, and soft tissue changes are checked during the examination before any new fitting surface is made.
What Denture Adhesive Can and Cannot Do
Denture adhesive creates a thin layer between the fitting surface and the gum that improves suction and reduces small movements. Used in modest amounts under a reasonably well-fitting denture, it is a legitimate supplement, and many people find it adds confidence while eating or speaking.
Its limits are clear. Adhesive cannot replace bone support that has been lost; if the ridge has resorbed substantially, the denture has nothing solid to rest on and the glue only holds it against a surface that no longer matches its shape. Adhesive does not slow resorption either, because the biological process continues underneath whether glue is used or not. It also does not meaningfully raise chewing force on a poorly supported denture, since the denture still tips and slides when force is applied off-centre. The worry that a denture might move during dinner or conversation tends to grow as the fit gets worse, and extra adhesive rarely settles it for long.
Home fixes carry their own risk. Do-it-yourself reline kits and soft pads sold in pharmacies can give a short improvement, but a layer applied without an impression of the ridge can change the bite, create pressure points and irritate the gum, and some materials damage the denture base. They also hide the underlying change for longer.
The practical rule is simple enough. When you notice that you need more adhesive than before, or need it where you did not before, the fit of the denture on the ridge should be examined. That examination decides whether a reline, a new denture or an implant-based option is the right next step.
Relining the Denture to the Current Ridge
Relining replaces the inner fitting surface of an existing denture with new material shaped to the ridge as it is today. When resorption has changed the ridge enough that the denture no longer sits accurately, a reline can restore the fit without making a whole new denture. There are three main types.
Chairside reline
A chairside, or direct, reline is carried out in the dental chair in a single visit. The dentist lines the fitting surface with a hard or soft reline material, seats the denture in the mouth while it sets, and trims it. The improvement is immediate, which makes this approach suitable for moderate fit discrepancies or as a temporary step while a longer plan is prepared.
Laboratory reline
In a laboratory reline, the dentist takes an impression of the current ridge using the denture itself as a tray, and a dental laboratory adds new acrylic to the fitting surface. The denture is usually away for a short time. This method is more precise than a chairside reline and generally lasts longer.
Soft reline
A soft reline uses a flexible, cushioning material in place of hard acrylic on the fitting surface. It is used for people whose gum over the ridge is thin or sensitive, where a hard surface causes sore spots. Soft materials need replacing more often because they harden and stain with time.
A reline works well when the discrepancy is moderate and the denture itself is structurally sound, with intact teeth, a stable bite and no cracks. It extends the useful life of the denture and usually reduces the need for adhesive substantially. It is less suited to extensive resorption or to a denture that is old and worn.
When a New Denture Is the Better Start
A denture made ten or more years ago was built for a ridge that no longer exists in that form. Relining such a denture has limited value, because the problem goes beyond the fitting surface; the teeth may be worn, the bite height may have dropped and the base may have distorted. In this situation the whole prosthesis is usually remade from fresh impressions of the current anatomy.
Data on how long complete dentures last in everyday care comes from large records studies. In a 20-year study of 187,227 publicly insured adults, complete dentures had a mean longevity of 6.06 years, and the authors concluded that they were commonly replaced after 6 years of service (PubMed 34645719). The same study found that pairs of complete dentures lasted longer than single dentures (PubMed 34645719). The timing for any one person varies widely with their rate of bone resorption, their saliva, their chewing habits and how the denture is cared for.
A new, well-fitting denture reduces adhesive needs substantially and improves comfort and chewing. It restores the correct bite height, which can also improve the support of the lips and lower face. What it does not do is stop resorption. The new denture will gradually loosen again over the following years for the same biological reasons, so it resets the clock on fit without removing the underlying process. For some people that reset is exactly what they need. For others, particularly those with a lower denture that has never been stable, it is a good moment to discuss whether implants could hold the new denture in place.
Implant-Retained Overdentures
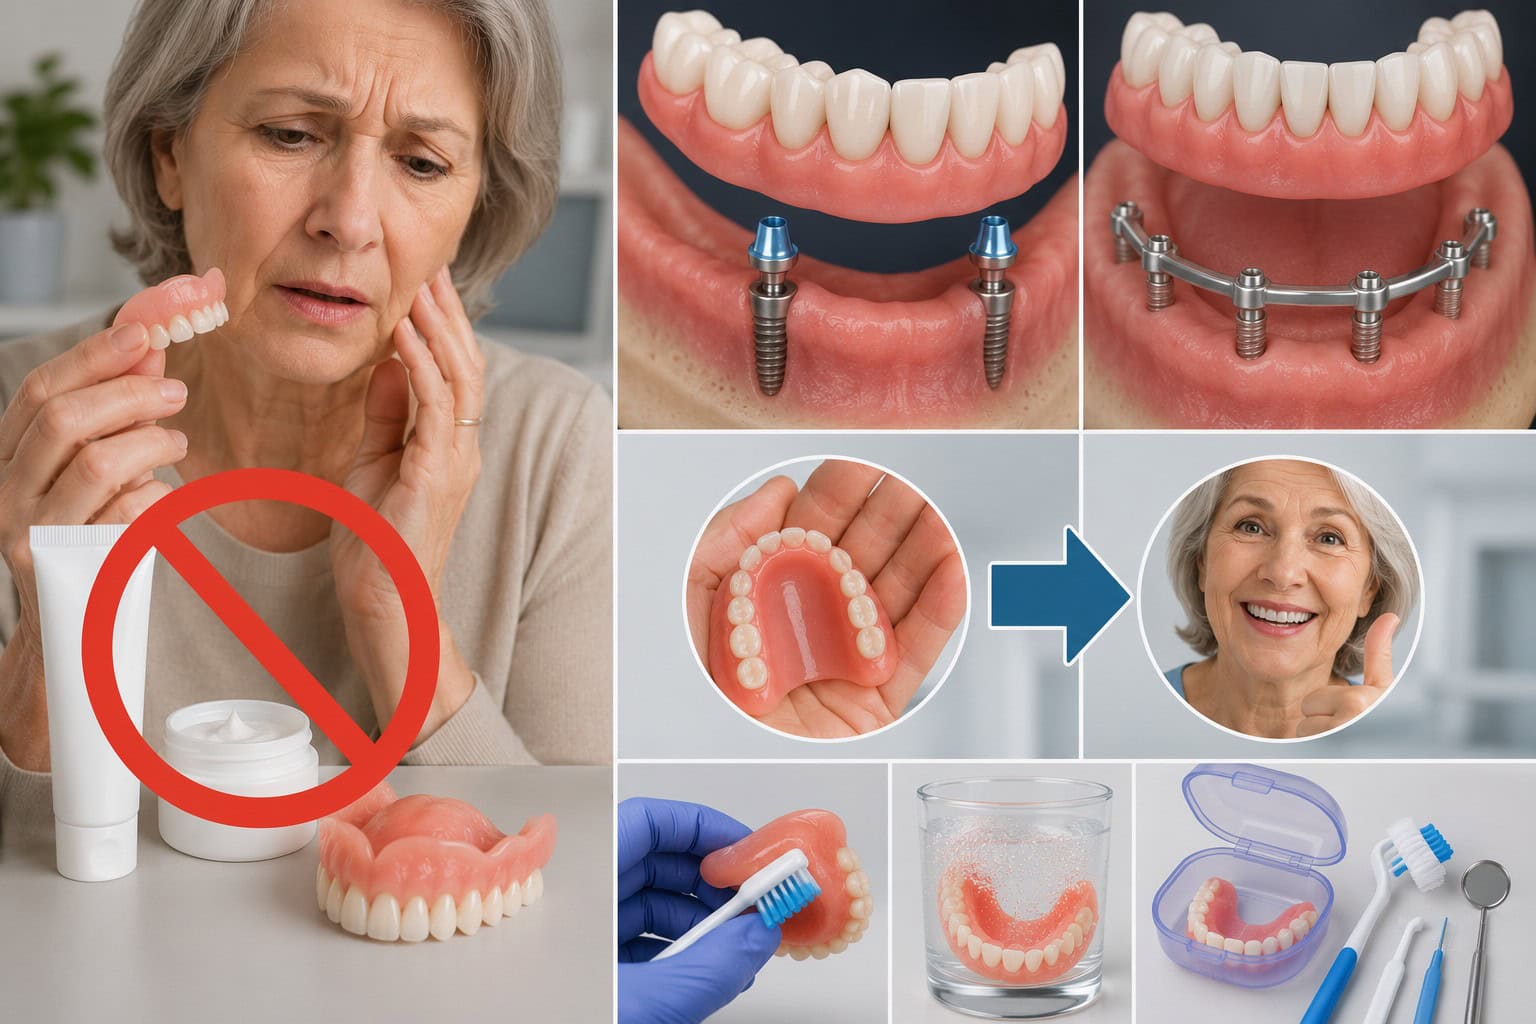
An implant-retained overdenture keeps the convenience of a removable denture and adds a mechanical connection that holds it firmly in place. Two to four dental implants are placed in the jawbone, and the denture is fitted with matching attachments such as snaps, a bar or locator attachments. During wear the denture clicks onto the implants instead of relying on suction and adhesive, and it still comes out for cleaning.
The difference for patients has been measured in a randomised trial. Sixty edentulous adults aged 65 to 75 received either a new conventional lower denture or a lower overdenture on two implants, and after 6 months general satisfaction in the implant group was approximately 36 percent higher (PubMed 14651229). The implant group also rated comfort, stability and ability to chew significantly higher (PubMed 14651229).
This approach suits the lower jaw particularly well. The lower ridge offers a small surface for suction, and the tongue and cheek muscles constantly push on the denture, so lower dentures are the ones most likely to need adhesive. The implants also load the bone at the sites where they are placed, which helps preserve bone locally.
An overdenture still needs daily care. In a study of 60 patients with denture stomatitis, poor denture hygiene, night-time wear and colonisation by Candida albicans, the yeast behind most oral thrush, were the significant factors (PubMed 27999492). Removing the denture at night, cleaning it and the attachments every day and brushing the gum and implant heads keep the tissue healthy and the attachments working.
Fixed Full-Arch Options, All-on-4 and All-on-6
For people whose priority is to stop removing their teeth altogether, a fixed implant-supported arch is the next step. In the All-on-4 approach, four implants are placed in the jaw, the two front ones upright and the two back ones angled, and together they support a complete fixed bridge. The bridge is screwed onto the implants and is removed only by the dentist during maintenance visits. There is no adhesive and no nightly removal, and the teeth stay in place during meals and conversation.
The angled back implants are planned to avoid anatomical structures such as the nerve in the lower jaw and the sinus in the upper jaw, which can allow a fixed arch in patients who would otherwise need bone grafting. Because the implants carry chewing forces into the bone, they help preserve the bone around them, although the ridge between implants can still change over time.
In suitable cases a fixed temporary bridge is attached on the same day as implant surgery, a method called immediate loading. Whether this is possible depends on how firmly the implants are anchored at placement, which the surgeon measures during the operation. The final bridge follows after the implants have integrated with the bone.
All-on-6 uses six implants instead of four. The extra implants spread the load over more anchor points, which can be preferred in people with strong bite forces, a large arch or anatomy where more support is useful. The choice between four and six implants is made on the three-dimensional scan, together with bone volume, bite and the planned bridge design. Both options need regular professional cleaning and checks of the screws and bridge.
Treatment When Bone Loss Is Advanced
People who have worn dentures for many years before considering implants often have substantial bone loss, more than would be present if implants had been placed soon after extraction. This does not automatically rule out implant treatment, but it may call for additional procedures.
Bone grafting
Bone grafting rebuilds lost bone volume using the patient's own bone, processed donor bone or synthetic graft material, often covered with a membrane. After a healing period, the grafted area can support conventional implant placement. Grafting adds time to treatment, and the size of the graft depends on how much height and width need to be restored.
Zygomatic implants
For severe bone loss in the upper jaw, zygomatic implants anchor in the cheekbone instead of the resorbed upper ridge, bypassing the missing bone. In very advanced cases this can avoid a large graft. It is a specialised procedure that requires careful three-dimensional planning.
These options mean that people who have been told they have too little bone for implants may still be candidates, subject to proper assessment. Mosdent's oral and maxillofacial surgery team evaluates complex bone loss cases with CBCT imaging and digital treatment planning before any surgical recommendation is made.
Long-term data supports implants as a durable option while showing why follow-up matters. A 20-year meta-analysis reported a mean implant survival rate of 92 percent in 3 prospective studies, falling to 78 percent after imputation, and 88 percent in 5 retrospective studies (PubMed 39305362). The authors stressed that follow-up is essential and should continue well after placement (PubMed 39305362). The bridge or denture on the implants usually needs maintenance or replacement sooner than the implants themselves.
Gum Health and the Assessment Before Any Fix
Whichever route is chosen, from a reline to a fixed arch, healthy gum tissue under and around the prosthesis is a condition for a good result. A loose denture that rocks on poorly supported tissue often causes low-grade gum inflammation, sore spots and overgrown tissue at the denture edges. Fitting a new surface over inflamed tissue records the swelling, and the fit changes again once it settles. Before any prosthetic adjustment or implant placement, a periodontal assessment confirms that the tissue is stable and healthy. At Mosdent, this assessment is a standard step in all prosthetic and implant planning.
The examination that decides between the options looks at several things together. The age and condition of the current denture, including cracks, tooth wear and bite height. How much the ridge has resorbed, assessed by hand and, when implants are considered, on a three-dimensional CBCT scan. The state of the gum and any signs of denture stomatitis. Saliva flow and the medicines you take. Finally, what you want from treatment, whether that is a denture that stays put with less glue, a removable denture that clicks into place or teeth that stay in permanently.
With those answers, the choice usually narrows quickly. A sound denture with moderate looseness is relined, an old or worn denture is remade, an unstable lower denture is a strong candidate for an overdenture, and people who want fixed teeth are assessed for All-on-4 or All-on-6. Mosdent has been treating international patients since 1992, and a chairside reline or an initial assessment can often be completed in a single visit. To discuss your situation, you can contact Mosdent.
Let’s plan the right treatment together.
Free Assessment→- 1.Tan WL, Wong TL, Wong MC, Lang NP. A systematic review of post-extractional alveolar hard and soft tissue dimensional changes in humans. Clin Oral Implants Res. 2012;23 Suppl 5:1-21. doi:10.1111/j.1600-0501.2011.02375.x. PubMed 22211303
- 2.Thomason JM, Lund JP, Chehade A, Feine JS. Patient satisfaction with mandibular implant overdentures and conventional dentures 6 months after delivery. Int J Prosthodont. 2003;16(5):467-473. PubMed 14651229
- 3.Aoun G, Cassia A. EVALUATION OF DENTURE-RELATED FACTORS PREDISPOSING TO DENTURE STOMATITIS IN A LEBANESE POPULATION. Mater Sociomed. 2016;28(5):392-396. PubMed 27999492
- 4.Stoopler ET, Villa A, Bindakhil M, Díaz DLO, Sollecito TP. Common Oral Conditions: A Review. JAMA. 2024;331(12):1045-1054. PubMed 38530258
- 5.Taylor M, Masood M, Mnatzaganian G. Complete denture replacement: a 20-year retrospective study of adults receiving publicly funded dental care. J Prosthodont Res 2022;66:452-458. PubMed 34645719
- 6.Kupka JR, König J, Al-Nawas B, Sagheb K, Schiegnitz E. How far can we go? A 20-year meta-analysis of dental implant survival rates. Clin Oral Investig 2024;28:541. PubMed 39305362